Questions as text
Q1 · Describe what psychologists have discovered about individual factors in changing health… 9990/32 Oct/Nov 2018
6 (a) Describe what psychologists have discovered about individual factors in changing health beliefs. [8] (b) Evaluate what psychologists have discovered about individual factors in changing health beliefs, including a discussion of individual and situational explanations. [10] Psychology and organisations Answer all questions.
18 marks
Mark scheme: 6(a) Describe what psychologists have discovered about individual factors 8 in changing health beliefs. Individual factors in changing health beliefs, including the following: • unrealistic optimism (Weinstein, 1980) • transtheoretical model (Prochaska et al., 1997) • health change in adolescents (Lau, 1990) Unrealistic optimism (Weinstein, 1980) Two studies. Study 1 found college students rated their own changes to be above average for experiencing positive events and below average for experiencing negative events from a list of 42. Study 2 asked students to list factors they thought would influence their own chances of experiencing 8 future events. When a second group of students read it they reported less unrealistic optimism for the same 8 events. This led the researchers to conclude that the unrealistic optimism was only experienced people focus on their own chances of achieving these outcomes and don’t realise that others may have just as many factors in their favour. Transtheoretical model (Prochaska et al., 1997) Health behaviour change involves progress through six stages of change: precontemplation, contemplation, preparation, action, maintenance, and termination. 10 processes identified to help individuals move from one stage to the next (e.g. self-liberation and helping relationships). Stagematched interventions (where the therapy matches the stage of change the patient is at) and proactive recruitment procedures have been to bring about dramatic improvements in recruitment, retention and progress towards change in health behaviours. Health change in adolescents (Lau, 1990) Longitudinal study of college students using self report questionnaires on health belief such as drinking, diet, exercise and wearing seat belts. Found peers do have a strong impact on the performance of health behaviours. But parents were more important as sources of influence over beliefs and behaviours. Mark according to the levels of response descriptors in Table A. Other appropriate responses should also be credited. 6(b) Evaluate what psychologists have discovered about individual factors 10 in changing health beliefs, including a discussion of individual and situational explanations. • Named issue – Individual and situational factors that could affect changing health beliefs. Weinstein offers both a situational and an individual explanation. The imagined future life events that could happen to people (e.g. living past 80) are situational but how we interpret these events are individual. In addition, whether a person believes these events will happen to them is individual. The stages of change a person will go through (Prochaska et al. – transtheoretical model) is individual. Each person will go through the stages in their own way and at their own rate. But they can be helped (or even hindered) through the stages by situational factors (e.g. the support of others). Lau looks at situational factors and the effects these have on health changes and beliefs in adolescents (e.g. the effects of parents and peers on health beliefs). • Usefulness (application of psychology to everyday life) of theories about individual factors in changing health beliefs – if we can discover the causes of the factors that people believe are affecting their health then we can challenge unhelpful beliefs via the media, doctors, parents, schools, universities, etc. • Generalisability of the samples used for the studies on individual factors – Lau’s study – students admitted to Carnegie Mellon University in Pittsburgh, PA. Weinstein also used college students • Evaluation of method for studies on individual factors (e.g. Reliability, validity, ethics, ecological validity) • Evaluation of data collection methods used for studies on individual factors – questionnaire data using quantitative methods collected by Lau and Weinstein Mark according to the levels of response descriptors in Table B. Other appropriate responses should also be credited. Psychology and organisations
This question in 9990/32 Oct/Nov 2018
Q2 · Explain what is meant by ‘fear arousal’ as a strategy for promoting health 9990/31 May/June 2019
5 (a) Explain what is meant by ‘fear arousal’ as a strategy for promoting health. [2] (b) Describe the Yale model of communication as a strategy for promoting health. [4] (c) Explain one strength and one weakness of the Yale model of communication as a strategy for promoting health. [6]
12 marks
Mark scheme: 5(a) Explain what is meant by 'fear arousal' as a strategy for promoting 2 health. Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: This is where the health promotion campaign uses a message that causes the public to feel afraid for their health and therefore makes changes in their lives to avoid this feared outcome. Other appropriate responses should also be credited. 5(b) Describe the Yale model of communication as a strategy for promoting 4 health. Award 1–2 marks for a basic answer with some understanding of the topic area. Likely to be a description of the model that is not linked to changing health behaviours. Award 3–4 marks for a detailed answer with clear understanding of the topic area. Can be awarded when specific examples or comments are made that link this model of communication as a way of changing health behaviours. For example: The message/the communication/the context – is it clear and direct, one or two sided, vivid and colourful? If is the clear and attention grabbing health message the person is more likely to pay attention to it (and this could then bring about change in their health behaviour) The medium – radio, TV, print, one-to-one, personal. This depends on the target audience. Health promotion aimed at young people could be best place on social media whereas older people might be better on TV or in the newspaper. The candidate could also consider the source/the communicator, the target/the audience or the situation. The candidate might also consider the stages of the process (e.g. attention, comprehension and acceptance/reaction). Other appropriate responses should also be credited. 5(c) Explain one strength and one weakness of the Yale model of 6 communication as a strategy for promoting health. Strengths could include • Less reductionist (holistic) nature of the theory • Practical application • Can be applied cross culturally Weaknesses could include • Lack of evidence to back up this model with reference to health promotion • Somewhat ethnocentric • Doesn’t explain how change in behaviour actually happens so could be considered to be less useful in terms of a strategy for promoting health Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will discuss one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will discuss one appropriate weakness in detail or one appropriate strength in detail. OR will discuss both one weakness and one strength in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt a discussion of either a strength or a weakness. This could include both but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) • No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/31 May/June 2019
Q3 · Explain what is meant by ‘fear arousal’ as a strategy for promoting health 9990/33 May/June 2019
5 (a) Explain what is meant by ‘fear arousal’ as a strategy for promoting health. [2] (b) Describe the Yale model of communication as a strategy for promoting health. [4] (c) Explain one strength and one weakness of the Yale model of communication as a strategy for promoting health. [6]
12 marks
Mark scheme: 5(a) Explain what is meant by 'fear arousal' as a strategy for promoting 2 health. Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: This is where the health promotion campaign uses a message that causes the public to feel afraid for their health and therefore makes changes in their lives to avoid this feared outcome. Other appropriate responses should also be credited. 5(b) Describe the Yale model of communication as a strategy for promoting 4 health. Award 1–2 marks for a basic answer with some understanding of the topic area. Likely to be a description of the model that is not linked to changing health behaviours. Award 3–4 marks for a detailed answer with clear understanding of the topic area. Can be awarded when specific examples or comments are made that link this model of communication as a way of changing health behaviours. For example: The message/the communication/the context – is it clear and direct, one or two sided, vivid and colourful? If is the clear and attention grabbing health message the person is more likely to pay attention to it (and this could then bring about change in their health behaviour) The medium – radio, TV, print, one-to-one, personal. This depends on the target audience. Health promotion aimed at young people could be best place on social media whereas older people might be better on TV or in the newspaper. The candidate could also consider the source/the communicator, the target/the audience or the situation. The candidate might also consider the stages of the process (e.g. attention, comprehension and acceptance/reaction). Other appropriate responses should also be credited. 5(c) Explain one strength and one weakness of the Yale model of 6 communication as a strategy for promoting health. Strengths could include • Less reductionist (holistic) nature of the theory • Practical application • Can be applied cross culturally Weaknesses could include • Lack of evidence to back up this model with reference to health promotion • Somewhat ethnocentric • Doesn’t explain how change in behaviour actually happens so could be considered to be less useful in terms of a strategy for promoting health Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will discuss one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will discuss one appropriate weakness in detail or one appropriate strength in detail. OR will discuss both one weakness and one strength in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt a discussion of either a strength or a weakness. This could include both but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) • No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/33 May/June 2019
Q4 · Explain what is meant by ‘open plan offices’ 9990/31 Oct/Nov 2019
7 (a) Explain what is meant by ‘open plan offices’. [2] (b) Describe the findings of the study by Cowpe (1989) of a safety promotion campaign to avoid chip pan fires. [4] (c) Explain one strength and one weakness of the study by Cowpe (1989) of a safety promotion campaign to avoid chip pan fires. [6]
12 marks
Mark scheme: 7(a) Explain what is meant by ‘open plan offices’. 2 Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: An office with no interior walls or low partitions (1), with no separate rooms or offices (1). Other appropriate responses should also be credited. 7(b) Describe the findings of the study by Cowpe (1989) of a safety promotion 4 campaign to avoid chip pan fires. Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: The results of the campaigns show 'net' declines in each area where the safety advertisements were shown of between 7 and 25% over a twelve-month period (2). The largest reduction in chip-pan fires was during the campaign (1). Questionnaires showed a significant increase in awareness of chip pan fires and safety measures to be taken – confidence in ability to cope with a chip-pan fire improved (1). The greatest change in chip-pan fire was reported during and immediately following the advertising campaign and this did reduce once the campaign had finished (1). Other appropriate responses should also be credited. 7(c) Explain one strength and one weakness of the study by Cowpe (1989) of a 6 safety promotion campaign to avoid chip pan fires. Strengths • Useful (applications to everyday life) as it shows the effectiveness of advertising campaigns and also the reduction in terms of cost to human life as well as the cost to the state for emergency services. • Good ecological validity as the advertisements were released as normal. • Good sample size – 5 regions in the UK. • Longitudinal so can investigate change in behaviour over time. • Quantitative data – can make comparisons between before and after the safety promotion campaign. • Data is from government/fire service statistics of chip pan fires reported so is free from experimenter bias. Weaknesses • Poor temporal validity as it was done in 1970s–1980s and in the modern day we have a lot more access to different types of media (also chip pans are not really used today). • Ethnocentric to the UK, there could have been other factors that led to the reduction in chip pan fires other than the advertising campaign (e.g. improvements in the safety features on the chip pan or less use of gas stoves). • Quantitative data – do not know the full reasoning behind the reduction in chip pan fires. • Some chip pan fires may not have been reported. Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will discuss one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will discuss one appropriate weakness in detail or one appropriate strength in detail. OR one weakness and one strength in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt a discussion of either a strength or a weakness. There could also be a discussion of both a strength and a weakness but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/31 Oct/Nov 2019
Q5 · Explain what is meant by ‘open plan offices’ 9990/32 Oct/Nov 2019
7 (a) Explain what is meant by ‘open plan offices’. [2] (b) Describe the findings of the study by Cowpe (1989) of a safety promotion campaign to avoid chip pan fires. [4] (c) Explain one strength and one weakness of the study by Cowpe (1989) of a safety promotion campaign to avoid chip pan fires. [6]
12 marks
Mark scheme: 7(a) Explain what is meant by ‘open plan offices’. 2 Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: An office with no interior walls or low partitions (1), with no separate rooms or offices (1). Other appropriate responses should also be credited. 7(b) Describe the findings of the study by Cowpe (1989) of a safety promotion 4 campaign to avoid chip pan fires. Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: The results of the campaigns show 'net' declines in each area where the safety advertisements were shown of between 7 and 25% over a twelve-month period (2). The largest reduction in chip-pan fires was during the campaign (1). Questionnaires showed a significant increase in awareness of chip pan fires and safety measures to be taken – confidence in ability to cope with a chip- pan fire improved (1). The greatest change in chip-pan fire was reported during and immediately following the advertising campaign and this did reduce once the campaign had finished (1). Other appropriate responses should also be credited. 7(c) Explain one strength and one weakness of the study by Cowpe (1989) of 6 a safety promotion campaign to avoid chip pan fires. Strengths • Useful (applications to everyday life) as it shows the effectiveness of advertising campaigns and also the reduction in terms of cost to human life as well as the cost to the state for emergency services. • Good ecological validity as the advertisements were released as normal. • Good sample size – 5 regions in the UK. • Longitudinal so can investigate change in behaviour over time. • Quantitative data – can make comparisons between before and after the safety promotion campaign. • Data is from government/fire service statistics of chip pan fires reported so is free from experimenter bias. Weaknesses • Poor temporal validity as it was done in 1970s–1980s and in the modern day we have a lot more access to different types of media (also chip pans are not really used today). • Ethnocentric to the UK, there could have been other factors that led to the reduction in chip pan fires other than the advertising campaign (e.g. improvements in the safety features on the chip pan or less use of gas stoves). • Quantitative data – do not know the full reasoning behind the reduction in chip pan fires. • Some chip pan fires may not have been reported. Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will discuss one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will discuss one appropriate weakness in detail or one appropriate strength in detail. OR one weakness and one strength in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt a discussion of either a strength or a weakness. There could also be a discussion of both a strength and a weakness but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/32 Oct/Nov 2019
Q6 · Explain what is meant by ‘open plan offices’ 9990/33 Oct/Nov 2019
7 (a) Explain what is meant by ‘open plan offices’. [2] (b) Describe the findings of the study by Cowpe (1989) of a safety promotion campaign to avoid chip pan fires. [4] (c) Explain one strength and one weakness of the study by Cowpe (1989) of a safety promotion campaign to avoid chip pan fires. [6]
12 marks
Mark scheme: 7(a) Explain what is meant by ‘open plan offices’. 2 Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: An office with no interior walls or low partitions (1), with no separate rooms or offices (1). Other appropriate responses should also be credited. 7(b) Describe the findings of the study by Cowpe (1989) of a safety promotion 4 campaign to avoid chip pan fires. Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: The results of the campaigns show 'net' declines in each area where the safety advertisements were shown of between 7 and 25% over a twelve-month period (2). The largest reduction in chip-pan fires was during the campaign (1). Questionnaires showed a significant increase in awareness of chip pan fires and safety measures to be taken – confidence in ability to cope with a chip- pan fire improved (1). The greatest change in chip-pan fire was reported during and immediately following the advertising campaign and this did reduce once the campaign had finished (1). Other appropriate responses should also be credited. 7(c) Explain one strength and one weakness of the study by Cowpe (1989) of 6 a safety promotion campaign to avoid chip pan fires. Strengths • Useful (applications to everyday life) as it shows the effectiveness of advertising campaigns and also the reduction in terms of cost to human life as well as the cost to the state for emergency services. • Good ecological validity as the advertisements were released as normal. • Good sample size – 5 regions in the UK. • Longitudinal so can investigate change in behaviour over time. • Quantitative data – can make comparisons between before and after the safety promotion campaign. • Data is from government/fire service statistics of chip pan fires reported so is free from experimenter bias. Weaknesses • Poor temporal validity as it was done in 1970s–1980s and in the modern day we have a lot more access to different types of media (also chip pans are not really used today). • Ethnocentric to the UK, there could have been other factors that led to the reduction in chip pan fires other than the advertising campaign (e.g. improvements in the safety features on the chip pan or less use of gas stoves). • Quantitative data – do not know the full reasoning behind the reduction in chip pan fires. • Some chip pan fires may not have been reported. Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will discuss one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will discuss one appropriate weakness in detail or one appropriate strength in detail. OR one weakness and one strength in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt a discussion of either a strength or a weakness. There could also be a discussion of both a strength and a weakness but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/33 Oct/Nov 2019
Q7 · Outline how Fox et al 9990/32 Feb/March 2020
5 (a) Outline how Fox et al. (1987) used a token economy in worksites to promote health. [2] (b) Describe the procedure of the ‘whole-school’ Food Dude programme from the study by Tapper et al. (2003). [4] (c) Explain one strength and one weakness of the study by Tapper et al. [6]
12 marks
Mark scheme: 5(a) Outline how Fox et al. (1987) used a token economy in worksites to 2 promote health. Award 1 mark for a basic outline of the term/concept. Award 2 marks for a detailed outline of the term/concept. For example: Fox et al. gave stamps for no lost-time injury (1). Stamps could be exchanged for items at redemption stores (1) Other appropriate responses should also be credited. 5(b) Describe the procedure of the ‘whole-school’ Food Dude programme 4 from the study by Tapper et al. (2003). Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: Children aged 4–11 watched the Food Dudes programme in lessons (1). They received rewards such as a Food Dudes sticker if they ate fruit and vegetables put out in front of them (1). They receive a Food Dude sticker for tasting a food (1), or a sticker and a small prize for eating a whole portion (1). The intervention phase was followed by a maintenance phase during which there are no videos and the letters and rewards became more intermittent (1). Additional content: Self reports were done with some of the parents to evaluate how many fruit and vegetables were consumed at home (1). Also credit the control group used during the later phases of the study where they just monitored consumption of fruit and vegetables when given extra fruit and vegetables that were delivered to the school during the duration of the study (1). Qualitative data was collected from both parents and teachers (1). Other appropriate responses should also be credited. 5(c) Explain one strength and one weakness of the study by Tapper et al. 6 Likely strengths include: • Wide age range of children studied (5–6 years, 2–4 years, 4–11 years) • Different types of studies done (e.g. some at home and some at school – nursery and primary school) • Both qualitative (e.g. enjoyment of the programme, enthusiasm for curriculum work, etc. and quantitative (number of fruit and vegetables eaten both at home and at school) data collected. Increases validity as can make comparisons as well as having detailed information on how the children responded to the programme. • Collected data from the teachers and parents which helps improve validity. • Highly ethical study as consent obtained from the parents and the school (and improved fruit and vegetable consumption which is a very good outcome for the children involved) • Provided training and all of the necessary equipment including the food to the schools • Good practical applications to be used in other schools. • Schools from a variety of locations in the UK (e.g. North Wales, Manchester, Oxfordshire, London) which improves generalisability. Likely weaknesses include: • Generalisability (UK) • Just based in primary schools so not sure if this would work with secondary school children or adults. • Could be an expensive programme to introduce in all schools so is less practical. • Social desirability and demand characteristics were possible as the participants may have told the researchers that the fruit and vegetable consumption increased when in fact either it had not or the participant/teacher/parent was not sure about the actual consumption. 5(c) Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will explain one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will explain one appropriate weakness in detail or one appropriate strength in detail. OR one weakness and one strength in less detail. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt an explanation of either a strength or a weakness. They could include both but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited
This question in 9990/32 Feb/March 2020
Q8 · Describe what psychologists have discovered about improving adherence to medical advice 9990/33 May/June 2020
6 (a) Describe what psychologists have discovered about improving adherence to medical advice. [8] (b) Evaluate what psychologists have discovered about improving adherence to medical advice, including a discussion about ethics. [10] Psychology and organisations Answer all questions.
18 marks
Mark scheme: 6(a) Describe what psychologists have discovered about improving 8 adherence to medical advice. Adherence to medical advice, including the following: • improve practitioner style (Ley, 1988) • behavioural techniques (Yokley and Glenwick, 1984; Watt et al., 2003) Improve practitioner style (Ley, 1988) Satisfaction – including listening to the patient and finding out what their worries are, etc. Understanding and memory – avoiding jargon, encouraging feedback to increase recall of instructions, etc. Selecting content – being aware of the effect of what they say to the patient (e.g. will it cause fear, is the patient particularly vulnerable), etc. Use simple language, state the key information first, repeat key points (by summarising). Behavioural techniques (Yokley and Glenwick, 1984) The aim was to evaluate the relative impact of four conditions for motivating parents to take their children to be immunised. The conditions were: • mailed general prompt • mailed specific prompt • mailed specific prompt plus expanded clinic hours (increased access, convenience condition) • mailed specific prompt plus monetary incentive (i.e. lottery) The target population consisted of children 5 years or younger who needed one or more inoculations for diphtheria, tetanus, polio etc. The entire population of a medium-sized mid-west city (population ~300 000) were used. The conditions in detail were: 1 General prompt group (195 participants) – general inoculation information and a prompt to get their child inoculated following 2 Specific prompt group (190 participants) – client specific inoculation information sent and told inoculations would be free. 3 Increased access group (185 participants) – also received a specific prompt and told about special extra clinic opening times. 4 Monetary incentive group (183 participants) – received specific prompt and told there would be cash prizes if they had their child inoculated 5 Contact control group (189 participants) – received telephone contact requesting basic information. 6 No contact group (191 participants) – no contact made with these families for the entire study. The impact of the different prompts was measured over the following 12 weeks to assess how many of each group would attend the clinics for the immunisation injections. The results showed that the monetary incentive group had the biggest impact on attendance, followed by the increased access group, specific prompt group and general prompt group respectively. Watt et al. (2003) A sample of 32 Australian children (10 male, 22 female, age range 1.5–6 years; mean age 3.2 years) suffering from asthma for a mean duration of 2.2 years. Questionnaires were completed after the use of the Breath-a-Tech (current market leader in Australia used as a ‘spacer’ for asthma drug dispensing) and then after use of the Funhaler over sequential two weeks. The Funhaler provides the child with an incentive to take their medication as correct usage ‘rewards’ the child with a spinning disc and a whistle. There was no significant difference in the quantity of medication delivered by the two devices. In terms of adherence to the drug, 38% more parents medicated their child on the previous day using the Funhaler compared to those using the standard Breath-a-Tech method. 60% more children adhered to the recommended dosage of four or more cycles of drug delivered with the Funhaler compared to the traditional method. Mark according to the levels of response descriptors in Table A. Other appropriate responses should also be credited. 6(b) Evaluate what psychologists have discovered about improving 10 adherence to medical advice, including a discussion about ethics. • Named issue – ethics The Watt et al. study was ethical as it asked for the parents of participants for informed consent and the children used the funhaler more during the study which helped their asthma. In the Yokley study they state: ‘The study dealt with the ethical issues involved in using control groups in immunization research by making control conditions essentially “delayed treatment” groups. Children in control conditions received motivational mailings after the study was completed.’ Although no direct consent was obtained, receiving reminders about immunisation is an everyday occurrence and the purpose of the study was to try and find ways of increasing immunisations in children. A range of other issues could be used for evaluation here. These include: • Generalisability • Usefulness (application of psychology to everyday life) • Evaluation of field method for studies • Reductionism • Determinism • Strengths and weaknesses with measuring the dependent variable. Mark according to the levels of response descriptors in Table B. Other appropriate responses should also be credited. Psychology and organisations Question Answer Marks
This question in 9990/33 May/June 2020
Q9 · Explain what is meant by ‘unrealistic optimism’ (Weinstein, 1980) in relation to… 9990/31 Oct/Nov 2020
5 (a) Explain what is meant by ‘unrealistic optimism’ (Weinstein, 1980) in relation to individual factors in changing health beliefs. [2] (b) Describe the procedure used in the study by Janis and Feshbach (1953) on fear arousal. [4] (c) Discuss two ethical issues in relation to the study by Janis and Feshbach. [6]
12 marks
Mark scheme: 5(a) Explain what is meant by ‘unrealistic optimism’ (Weinstein, 1980) in relation to individual factors in changing health beliefs. Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: Unrealistic optimism is an error of judgment where individuals perceive others to be of greater risk of illness and harm than themselves (1). Individuals see themselves as invulnerable to disease (1). Other appropriate responses should also be credited. 5(b) Describe the procedure used in the study by Janis and Feshbach (1953) on fear arousal. Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: Independent groups design experiment using 200 High School students (mean age 15 years) each exposed to lecture and administration of questionnaire to record emotional reactions 3 times. Group 1 (50) – High Fear Arousal Group – given lecture on dental hygiene and its effects including slides showing diseased mouths and explanation of diseases including cancer and consequences. Group 2 (50) – Moderate Fear Arousal Group – given similar lecture as group one and similar picture but less disturbing. Group 3 (50) – Minimal Fear Arousal Group – Lecture about teeth and cavities, without pictures or consequences. Control group (50) – given lecture about the structure of the human eye. Questionnaire given one week before lecture, after lecture and one week after lecture to gauge emotional reaction and level of conformity. Other appropriate responses should also be credited 4 Question Answer Marks 5(c) Discuss two ethical issues in relation to the study by Janis and Feshbach. Candidates will most likely refer to the following: • Protection from harm – those in high or moderate fear arousal condition may have been distressed seeing pictures and hearing explanations of serious illnesses. Furthermore, those in the high arousal group may be so affected that they could be less likely to visit the dentist as a result. • Lack of informed consent – students only around 15 years old. It is not clear if students gave consent or if consent was given for them. This may raise further issues of deception and protection if they or their parents were not given all the information about what they were going to be experiencing. • Confidentiality – participants’ names and other identifiers protected by researchers. • Deception – it could be argued that the extreme descriptions in the high fear arousal group were due to other factors other than simply hygiene (smoking, for example) so misleading. • Right of withdrawal – as the participants are high school students and attending a lecture they may feel that they have to continue with the study. • Debrief – candidates may discuss the value of a debrief in relation to the study despite not being evidenced in the paper. Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will include at least two points. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will include one appropriate point in detail or at least two points in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt to describe a point. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited. 6
This question in 9990/31 Oct/Nov 2020
Q10 · Explain what is meant by ‘unrealistic optimism’ (Weinstein, 1980) in relation to… 9990/33 Oct/Nov 2020
5 (a) Explain what is meant by ‘unrealistic optimism’ (Weinstein, 1980) in relation to individual factors in changing health beliefs. [2] (b) Describe the procedure used in the study by Janis and Feshbach (1953) on fear arousal. [4] (c) Discuss two ethical issues in relation to the study by Janis and Feshbach. [6]
12 marks
Mark scheme: 5(a) Explain what is meant by ‘unrealistic optimism’ (Weinstein, 1980) in relation to individual factors in changing health beliefs. Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: Unrealistic optimism is an error of judgment where individuals perceive others to be of greater risk of illness and harm than themselves (1). Individuals see themselves as invulnerable to disease (1). Other appropriate responses should also be credited. 5(b) Describe the procedure used in the study by Janis and Feshbach (1953) on fear arousal. Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: Independent groups design experiment using 200 High School students (mean age 15 years) each exposed to lecture and administration of questionnaire to record emotional reactions 3 times. Group 1 (50) – High Fear Arousal Group – given lecture on dental hygiene and its effects including slides showing diseased mouths and explanation of diseases including cancer and consequences. Group 2 (50) – Moderate Fear Arousal Group – given similar lecture as group one and similar picture but less disturbing. Group 3 (50) – Minimal Fear Arousal Group – Lecture about teeth and cavities, without pictures or consequences. Control group (50) – given lecture about the structure of the human eye. Questionnaire given one week before lecture, after lecture and one week after lecture to gauge emotional reaction and level of conformity. Other appropriate responses should also be credited 4 Question Answer Marks 5(c) Discuss two ethical issues in relation to the study by Janis and Feshbach. Candidates will most likely refer to the following: • Protection from harm – those in high or moderate fear arousal condition may have been distressed seeing pictures and hearing explanations of serious illnesses. Furthermore, those in the high arousal group may be so affected that they could be less likely to visit the dentist as a result. • Lack of informed consent – students only around 15 years old. It is not clear if students gave consent or if consent was given for them. This may raise further issues of deception and protection if they or their parents were not given all the information about what they were going to be experiencing. • Confidentiality – participants’ names and other identifiers protected by researchers. • Deception – it could be argued that the extreme descriptions in the high fear arousal group were due to other factors other than simply hygiene (smoking, for example) so misleading. • Right of withdrawal – as the participants are high school students and attending a lecture they may feel that they have to continue with the study. • Debrief – candidates may discuss the value of a debrief in relation to the study despite not being evidenced in the paper. Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will include at least two points. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will include one appropriate point in detail or at least two points in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt to describe a point. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited. 6
This question in 9990/33 Oct/Nov 2020
Q11 · Identify one physical and one psychological work condition 9990/32 Feb/March 2021
7 (a) Identify one physical and one psychological work condition. [2] (b) Cowpe (1989) tested a safety promotion campaign. Describe this safety promotion campaign. [4] (c) Explain one strength and one weakness of this safety promotion campaign. [6]
12 marks
Mark scheme: 7(a) Identify one physical and one psychological work condition. 2 Award 1 mark for a basic explanation of the term/concept.- 1 identified. Award 2 marks for a detailed explanation of the term/concept. – 2 identified. For example: Physical – layout of the office/factory, shift timings, open plan offices, etc. Psychological – how you feel about how your colleagues treat you at work, motivation, satisfaction, how you feel about being bullied, etc. Other appropriate responses should also be credited. 7(b) Cowpe (1989) tested a safety promotion campaign. 4 Describe this safety promotion campaign. Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: 60 second adverts shown on television (1), Showed the initial causes of the fire (over-filling and in-attendance) (1), then showed the actions required to put the chip pan fire out (1) e.g. turn off the heat, cover the pan with a damp cloth or leave the pan to cool down (1 mark each up to a maximum of 2) Shown on ten regional television areas in UK from 1976–1984. (1) Other appropriate responses should also be credited. 7(c) Explain one strength and one weakness of this safety promotion 6 campaign. Likely strengths include – • Cowpe considered a number of strategies before deciding on the containment strategy (credit references to why prevention strategy was rejected) • Shown over a number of years – strengths of longitudinal research – can check that the campaign has continued to have an effect on reducing chip pan fires in the long term. • Shown in a variety of places so has fairly good population validity and can be more certain this strategy would work in other parts of the UK • Good practical applications for showing health and safety promotion advertising on television. Although the effect decayed over time, the cost of the advertising concluded to be worth it due to the reduction in loss of life and property. Likely weaknesses include – • Ethnocentric to the UK where the advertising campaign might be more effective as most people have access to a television. • Lacks temporal validity as people no longer have chip pans and this wouldn’t tell us if we could prevent other types of fires using a similar advertising campaign. Also many people do not watch advertising in the same way as we can skip through advertising when watching television/internet videos. • Lacks qualitative data. We do not know why the fires stopped or if it was the advertising that caused the reduction in the fires as just quantitative data was collected. Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will explain one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will explain one appropriate weakness in detail or one appropriate strength in detail. OR one weakness and one strength in less detail. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt an explanation of either a strength or a weakness. They could include both but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/32 Feb/March 2021
Q12 · Describe what psychologists have discovered about strategies for promoting health 9990/32 May/June 2021
6 (a) Describe what psychologists have discovered about strategies for promoting health. [8] (b) Evaluate what psychologists have discovered about strategies for promoting health, including a discussion of the longitudinal research method. [10] Psychology and organisations Answer all questions.
18 marks
Mark scheme: 6(a) Describe what psychologists have discovered about strategies for 8 promoting health. Strategies for promoting health, including the following • fear arousal (Janis and Feshbach, 1953; Cowpe, 1989) • Yale model of communication • providing information (Lewin, 1992) Fear arousal – Janis and Feshback, 1953 Independent groups design experiment using 200 High School students (mean age 15 years) each exposed to lecture and administration of questionnaire to record emotional reactions 3 times. Group 1 (50) – High Fear Arousal Group – given lecture on dental hygiene and its effects including slides showing diseased mouths and explanation of diseases including cancer and consequences. Group 2 (50) – Moderate Fear Arousal Group – given similar lecture as group one and similar picture but less disturbing. Group 3 (50) – Minimal Fear Arousal Group – Lecture about teeth and cavities, without pictures or consequences. Control group (50) – given lecture about the structure of the human eye. Questionnaire given one week before lecture, after lecture and one week after lecture to gauge emotional reaction and level of conformity. Minimal fear arousal most effective in encouraging students to adopt the oral hygiene recommendations. Fear arousal – Cowpe, 1989 Aim was to test effectiveness of advertising campaign. Two 60 second adverts made showing the cause of chip pan fires (overfilling and inattendance). Shown in ten UK regions between 1976–1984. 12% drop in fires and high levels of awareness of the dangers of chip pan fires reported. Yale model of communication The source/the communicator – who is giving the message; are they credible, trustworthy? If a trustworthy person such as a doctor or scientist is giving the information to the person this is more likely to bring about behaviour change. The message/the communication/the context – is it clear and direct, one or two sided, vivid and colourful? If is the clear and attention-grabbing health message the person is more likely to pay attention to it (and this could then bring about change in their health behaviour) The medium – radio, TV, print, one-to-one, personal. This depends on the target audience. Health promotion aimed at young people could be best place on social media whereas older people might be better on TV or in the newspaper. The target/the audience – Who is the message aimed at? Is the audience sympathetic, knowledgeable? If the audience is not knowledgeable it is best to keep the message simple or show images (such as with a stopping smoking campaign that shows images of the damage caused by smoking). 6(a) The situation – where will the message be received, home, cinema, doctors? Where are the people most likely to be receptive to the health promotion message? Is it when they feel relaxed at home or when they are thinking about their health behaviour, e.g. at the doctor’s surgery. The candidate might also consider the stages of the process (e.g. attention, comprehension and acceptance/reaction). Providing information – Lewin, 1992 – (not 2002) 176 patients who recently suffered a heart attack were randomly allocated to either 1) self-help rehab programme 2) standard care plus a placebo package of information and informal counselling. Psychological adjustments better in the rehab group at one year. Significantly fewer appointments with GPs and fewer readmitted to hospital in first six months. Mark according to the levels of response descriptors in Table A. Other appropriate responses should also be credited. 6(b) Evaluate what psychologists have discovered about strategies for 10 promoting health, including a discussion of the longitudinal research method. A range of issues could be used for evaluation here. These include: • Named issue – Longitudinal – Strengths include that it shows change in behaviour over time, often can get more detail due to the length of time spent with participants. Weaknesses include that it involves a lot of commitment/time/cost of the psychologist and their university/funding body and participant attrition. Cowpe study took place over from 1976–1984. Lewin 1992 – over six months, Lewin 2002 – over 13 months. Likely to argue that Janis and Feshbeck is snapshot as just over a week so cannot measure long term changes in behaviour. • Usefulness • Generalisability of the samples used in the studies. • Qualitative and quantitative data collection methods • Ecological validity of the studies. • Holistic nature of Yale Model of Communication • Individual vs situational explanations Mark according to the levels of response descriptors in Table B. Other appropriate responses should also be credited. Psychology and organisations
This question in 9990/32 May/June 2021
Q13 · Outline the Yale model of communication in relation to health promotion 9990/31 Oct/Nov 2021
5 (a) Outline the Yale model of communication in relation to health promotion. [2] (b) Describe the study by Lau et al. (1990) on health change in adolescents. [4] (c) Explain one strength and one weakness of the study by Lau et al. [6]
12 marks
Mark scheme: 5(a) Outline the Yale model of communication in relation to health 2 promotion. Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: There are 3 main stages in the Yale model of communication. These are attention (the message must be attention-grabbing so person reads health advice), (2) comprehension (message must be understood so people understand health advice given) (2), and acceptance (although the recipient does not need to believe the message, they do need to accept it and change health behaviours accordingly). (2) Other appropriate responses should also be credited. 5(b) Describe the study by Lau et al. (1990) on health change in adolescents. 4 Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: A longitudinal study that aimed to explore the influences (peers and/or parents) and changes in young people’s preventive health beliefs and behaviours regarding drinking, diet, exercise and wearing seatbelts. (1) Participants were over 1000 students from Carnegie Mellon University. (1) Data gathered via questionnaire from student and their parents (baseline views) and again in the Spring of both Year 2 and Year 3 at university. (1) The findings were that parents provided the greatest influence on young peoples’ health preventive beliefs and practices (with modelling being the most powerful influence). (1) Views changed significantly during the study as the influence of peers increased. (1) Once the young person leaves home, their peers have a stronger influence over their health behaviour. (1) Other appropriate responses should also be credited. 5(c) Explain one strength and one weakness of the study by Lau et al. 6 Likely strengths are • Longitudinal study allows change to be seen in specific participants • Use of questionnaires to collect a large amount of data easily • Data from both parent and student (rather than simply asking student what they think their parent’s views are) • Variety of health prevention measures looked at (drinking, diet, exercise and wearing seatbelts) Likely weaknesses are • Unrepresentative nature of sample (well-educated and affluent students on the whole; significant imbalance in gender with far fewer females than males) • Reliance on self-report as students may lie, particularly with regard to reporting amount of drinking. • Attrition rate high with 1029 at outset, 635 in year 2 and 532 in year 3. • Lack of temporal validity (adolescents in study are now in their mid 50s) Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will explain one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will explain one appropriate weakness in detail or one appropriate strength in detail. OR one weakness and one strength in less detail. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt an explanation of either a strength or a weakness. They could include both but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/31 Oct/Nov 2021
Q14 · Outline the Yale model of communication in relation to health promotion 9990/33 Oct/Nov 2021
5 (a) Outline the Yale model of communication in relation to health promotion. [2] (b) Describe the study by Lau et al. (1990) on health change in adolescents. [4] (c) Explain one strength and one weakness of the study by Lau et al. [6]
12 marks
Mark scheme: 5(a) Outline the Yale model of communication in relation to health 2 promotion. Award 1 mark for a basic explanation of the term/concept. Award 2 marks for a detailed explanation of the term/concept. For example: There are 3 main stages in the Yale model of communication. These are attention (the message must be attention-grabbing so person reads health advice), (2) comprehension (message must be understood so people understand health advice given) (2), and acceptance (although the recipient does not need to believe the message, they do need to accept it and change health behaviours accordingly). (2) Other appropriate responses should also be credited. 5(b) Describe the study by Lau et al. (1990) on health change in adolescents. 4 Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. For example: A longitudinal study that aimed to explore the influences (peers and/or parents) and changes in young people’s preventive health beliefs and behaviours regarding drinking, diet, exercise and wearing seatbelts. (1) Participants were over 1000 students from Carnegie Mellon University. (1) Data gathered via questionnaire from student and their parents (baseline views) and again in the Spring of both Year 2 and Year 3 at university. (1) The findings were that parents provided the greatest influence on young peoples’ health preventive beliefs and practices (with modelling being the most powerful influence). (1) Views changed significantly during the study as the influence of peers increased. (1) Once the young person leaves home, their peers have a stronger influence over their health behaviour. (1) Other appropriate responses should also be credited. 5(c) Explain one strength and one weakness of the study by Lau et al. 6 Likely strengths are • Longitudinal study allows change to be seen in specific participants • Use of questionnaires to collect a large amount of data easily • Data from both parent and student (rather than simply asking student what they think their parent’s views are) • Variety of health prevention measures looked at (drinking, diet, exercise and wearing seatbelts) Likely weaknesses are • Unrepresentative nature of sample (well-educated and affluent students on the whole; significant imbalance in gender with far fewer females than males) • Reliance on self-report as students may lie, particularly with regard to reporting amount of drinking. • Attrition rate high with 1029 at outset, 635 in year 2 and 532 in year 3. • Lack of temporal validity (adolescents in study are now in their mid 50s) Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will explain one strength and one weakness. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will explain one appropriate weakness in detail or one appropriate strength in detail. OR one weakness and one strength in less detail. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt an explanation of either a strength or a weakness. They could include both but just as an attempt. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/33 Oct/Nov 2021
Q15 · Describe what psychologists have discovered about individual factors in changing health… 9990/32 May/June 2022
6 (a) Describe what psychologists have discovered about individual factors in changing health beliefs (unrealistic optimism, transtheoretical model, health change in adolescents). [8] (b) Evaluate what psychologists have discovered about individual factors in changing health beliefs (unrealistic optimism, transtheoretical model, health change in adolescents), including a discussion of practical applications. [10] Psychology and organisations Answer all questions.
18 marks
Mark scheme: 6(a) Describe what psychologists have discovered about individual factors in changing health beliefs (unrealistic optimism, transtheoretical model, health change in adolescents). Individual factors in changing health beliefs, including the following: unrealistic optimism (Weinstein, 1980) transtheoretical model (Prochaska et al., 1997) health change in adolescents (Lau, 1990) Unrealistic optimism (Weinstein, 1980) Study 1 – 258 college students completed a self-report. Given 42 life events and indicated the likelihood of experiencing the event on a 15 point scale. Results were that the college students rated their own chances to be above average for experiencing positive events and below average for experiencing negative events. Study 2 – asked students to list factors they thought would influence their own chances of experiencing 8 future events. When a second group of students read it they reported less unrealistic optimism for the same 8 events. This led the researchers to conclude that the unrealistic optimism was only experienced when people focus on their own chances of achieving these outcomes and don’t realise that others may have just as many factors in their favour. Transtheoretical model (Prochaska et al., 1997) Health behaviour change involves progress through six stages of change: pre-contemplation, contemplation, preparation, action, maintenance, and termination. 10 processes identified to help individuals move from one stage to the next (e.g., self-liberation and helping relationships). Stage matched interventions (where the therapy matches the stage of change the patient is at) and proactive recruitment procedures have been to bring about dramatic improvements in recruitment, retention and progress towards change in health behaviours. Health change in adolescents (Lau, 1990) Longitudinal study of 947 college students + parents from Carnegie Mellon University using self-report questionnaires on health belief such as drinking, diet, exercise and wearing seat belts. Substantial change in health behaviours during the first three years of college. Peers have an increasing influence on the participants. But parents were more important as sources of influence over beliefs and behaviours. Direct modelling from both peers and parents had greatest effect on health behaviour. Mark according to the levels of response descriptors in Table A. Other appropriate responses should also be credited. Question Answer Marks 6(b) Evaluate what psychologists have discovered about individual factors in changing health beliefs (unrealistic optimism, transtheoretical model, health change in adolescents), including a discussion of practical applications. Named issue – Practical applications of theories about individual factors in changing health beliefs – if we can discover the causes of the factors that people believe are affecting their health then we can challenge unhelpful beliefs via the media, doctors, parents, schools, universities, etc. e.g. Weinstein – could do a leaflet campaign of college students to make them aware of the risks, Prochaska – can tailor treatment to the stage that the individual is at, Lau – can target parents and make them aware of the effects of their behaviour on the health views of the adolescents, could run lessons at school to make students aware of the effects of their own health beliefs on their peers. Individual versus situational factors Generalisability of the samples used for the studies on individual factors Evaluation of method for studies on individual factors (e.g. reliability, validity, ethics, ecological validity) Evaluation of data collection methods used for studies on individual factors Mark according to the levels of response descriptors in Table B. Other appropriate responses should also be credited. 10
This question in 9990/32 May/June 2022
Q16 · Identify two of the measures used in the five-city project on health promotion in… 9990/31 Oct/Nov 2022
5 (a) Identify two of the measures used in the five-city project on health promotion in communities (Farquhar et al., 1985). [2] (b) Describe the study on health promotion in worksites by Fox et al. (1987). [4] (c) Explain one strength and one weakness of longitudinal research, using the study by Fox et al. as an example. [6]
12 marks
Mark scheme: 5(a) Identify two of the measures used in the five-city project on health 2 promotion in communities (Farquhar et al., 1985). Award 1 mark for each correctly identified item. Most likely answers: • Height • Weight • Obesity • Blood pressure • Resting heart rate • Smoking • Stress • Mortality Other appropriate responses should also be credited. 5(b) Describe the study on health promotion in worksites by Fox et al., 4 (1987). Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. A token economy that used trading stamps as tokens (1) was instituted at two dangerous open-pit mines (1). Employees earned stamps for working without lost-time injuries, for being in work groups in which all other workers had no lost-time injuries, for not being involved in equipment-damaging accidents, for making adopted safety suggestions, and for unusual behaviour which prevented an injury or accident (2). They lost stamp awards if they or other workers in their group were injured, caused equipment damage, or failed to report accidents or injuries (1). The stamps could be exchanged for a selection of thousands of items at redemption stores (1). Implementation of the token economy was followed by large reductions in the number of days lost from work because of injuries, the number of lost- time injuries, and the costs of accidents and injuries (1). The reductions in costs far exceeded the costs of operating the token economy (1). All improvements were maintained over several years (1). Other appropriate responses should also be credited. 5(c) Explain one strength and one weakness of longitudinal research, 6 using the study by Fox et al. as an example. Strengths could include: • That changes in behaviour can be seen over time enabling the success of the token economy system to be seen long-term rather than just when scheme is introduced • Continuing to collect data increases validity of findings as it enables any fluctuations to be seen as other factors may change e.g. changes to management, difficulties in mining in specific regions etc. • The overall cost over time of the scheme weighed against the money saved in the long-term by the reduction in accidents and days off • To be able to adjust the value of the tokens, seeing the effect of this. This could either be to increase in line with inflation or to reduce to see if the motivation continues to work at reduced cost to mine Likely weaknesses include: • Problems of attrition. One mine did close during the course of the study (though after a number of years) • Employees may leave or join within the study and some may be motivated more or less by the token economy • Cost of carrying out research over an extended period of time Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will discuss at least two points regarding longitudinal research. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will discuss one point about longitudinal research in detail or two or more in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt a discussion. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/31 Oct/Nov 2022
Q17 · Identify two of the measures used in the five-city project on health promotion in… 9990/33 Oct/Nov 2022
5 (a) Identify two of the measures used in the five-city project on health promotion in communities (Farquhar et al., 1985). [2] (b) Describe the study on health promotion in worksites by Fox et al. (1987). [4] (c) Explain one strength and one weakness of longitudinal research, using the study by Fox et al. as an example. [6]
12 marks
Mark scheme: 5(a) Identify two of the measures used in the five-city project on health 2 promotion in communities (Farquhar et al., 1985). Award 1 mark for each correctly identified item. Most likely answers: • Height • Weight • Obesity • Blood pressure • Resting heart rate • Smoking • Stress • Mortality Other appropriate responses should also be credited. 5(b) Describe the study on health promotion in worksites by Fox et al., 4 (1987). Award 1–2 marks for a basic answer with some understanding of the topic area. Award 3–4 marks for a detailed answer with clear understanding of the topic area. A token economy that used trading stamps as tokens (1) was instituted at two dangerous open-pit mines (1). Employees earned stamps for working without lost-time injuries, for being in work groups in which all other workers had no lost-time injuries, for not being involved in equipment-damaging accidents, for making adopted safety suggestions, and for unusual behaviour which prevented an injury or accident (2). They lost stamp awards if they or other workers in their group were injured, caused equipment damage, or failed to report accidents or injuries (1). The stamps could be exchanged for a selection of thousands of items at redemption stores (1). Implementation of the token economy was followed by large reductions in the number of days lost from work because of injuries, the number of lost- time injuries, and the costs of accidents and injuries (1). The reductions in costs far exceeded the costs of operating the token economy (1). All improvements were maintained over several years (1). Other appropriate responses should also be credited. 5(c) Explain one strength and one weakness of longitudinal research, 6 using the study by Fox et al. as an example. Strengths could include: • That changes in behaviour can be seen over time enabling the success of the token economy system to be seen long-term rather than just when scheme is introduced • Continuing to collect data increases validity of findings as it enables any fluctuations to be seen as other factors may change e.g. changes to management, difficulties in mining in specific regions etc. • The overall cost over time of the scheme weighed against the money saved in the long-term by the reduction in accidents and days off • To be able to adjust the value of the tokens, seeing the effect of this. This could either be to increase in line with inflation or to reduce to see if the motivation continues to work at reduced cost to mine Likely weaknesses include: • Problems of attrition. One mine did close during the course of the study (though after a number of years) • Employees may leave or join within the study and some may be motivated more or less by the token economy • Cost of carrying out research over an extended period of time Mark according to the levels of response criteria below: Level 3 (5–6 marks) • Candidates will show a clear understanding of the question and will discuss at least two points regarding longitudinal research. • Candidates will provide a good explanation with clear detail. Level 2 (3–4 marks) • Candidates will show an understanding of the question and will discuss one point about longitudinal research in detail or two or more in less detail. • Candidates will provide a good explanation. Level 1 (1–2 marks) • Candidates will show a basic understanding of the question and will attempt a discussion. • Candidates will provide a limited explanation. Level 0 (0 marks) No response worthy of credit. Other appropriate responses should also be credited.
This question in 9990/33 Oct/Nov 2022
Q18 · Describe what psychologists have discovered about strategies for promoting health (fear… 9990/31 Oct/Nov 2023
6 (a) Describe what psychologists have discovered about strategies for promoting health (fear arousal, Yale model of communication, providing information). [8] (b) Evaluate what psychologists have discovered about strategies for promoting health (fear arousal, Yale model of communication, providing information), including a discussion of quantitative and qualitative data. [10] Psychology and organisations Answer all questions.
18 marks
Mark scheme: 6(a) Describe what psychologists have discovered about 8 strategies for promoting health (fear arousal, Yale model of communication, providing information). Strategies for promoting health, including the following • fear arousal (Janis and Feshbach, 1953; Cowpe, 1989) • Yale model of communication • providing information (Lewin, 1992) Fear arousal – Janis and Feshbach, 1953 Independent groups design experiment using 200 High School students (mean age 15 years) each exposed to lecture and administration of questionnaire to record emotional reactions 3 times. Group 1 (50) – High Fear Arousal Group – given lecture on dental hygiene and its effects including slides showing diseased mouths and explanation of diseases including cancer and consequences. Group 2 (50) – Moderate Fear Arousal Group – given similar lecture as group one and similar picture but less disturbing. Group 3 (50) – Minimal Fear Arousal Group – Lecture about teeth and cavities, without pictures or consequences. Control group (50) – given lecture about the structure of the human eye. Questionnaire given one week before lecture, after lecture and one week after lecture to gauge emotional reaction and level of conformity. Minimal fear arousal most effective in encouraging students to adopt the oral hygiene recommendations. 6(a) Fear arousal – Cowpe, 1989 Aim was to test effectiveness of advertising campaign. Two 60 second adverts made showing the cause of chip pan fires (overfilling and inattendance). Shown in ten UK regions between 1976–1984. 12% drop in fires and high levels of awareness of the dangers of chip pan fires reported. Yale model of communication The source/the communicator – who is giving the message; are they credible, trustworthy? If a trustworthy person such as a doctor or scientist is giving the information to the person this is more likely to bring about behaviour change. The message / the communication / the context – is it clear and direct, one or two sided, vivid and colourful? If is the clear and attention-grabbing health message the person is more likely to pay attention to it (and this could then bring about change in their health behaviour). The medium – radio, TV, print, one-to-one, personal. This depends on the target audience. Health promotion aimed at young people could be best place on social media whereas older people might be better on TV or in the newspaper. The target / the audience – Who is the message aimed at? Is the audience sympathetic, knowledgeable? If the audience is not knowledgeable it is best to keep the message simple or show images (such as with a stopping smoking campaign that shows images of the damage caused by smoking). 6(a) The situation – where will the message be received, home, cinema, doctors? Where are the people most likely to be receptive to the health promotion message? Is it when they feel relaxed at home or when they are thinking about their health behaviour (e.g. at the doctor’s surgery). The candidate might also consider the stages of the process (e.g. attention, comprehension and acceptance/reaction). Providing information – Lewin, 1992 – (not 2002) 176 patients recently suffered a heart attack were randomly allocated to either 1) self-help rehab programme 2) standard care plus a placebo package of information and informal counselling. Psychological adjustments better in the rehab group at one year. Significantly less appointments with GPs and fewer readmitted to hospital in first six months. Mark according to the levels of response descriptors in Table A. Other appropriate responses should also be credited. 6(b) Evaluate what psychologists have discovered about 10 strategies for promoting health (fear arousal, Yale model of communication, providing information), including a discussion of quantitative and qualitative data. A range of issues could be used for evaluation here. These include: • Named issue – quantitative and qualitative data Quantitative data in Cowpe (percentage of decrease in chip pan fires), Quantative data collected from a variety of sources in Lewin et al. study. Quantitative in Janis and Feshbeck e.g. % of students who had changed their tooth brushing behaviour. Social desirability in the Lewin study and Janis and Feshbeck due to self-report measures used. Lack of social desirability in Cowpe as this was secondary data from government statistics of chip pan fires. Strengths and weaknesses of quantitative/qualitative data • Longitudinal research • Usefulness • Generalisability of the samples used in the studies. • Ecological validity of the studies. • Holistic nature of Yale Model of Communication • Individual vs situational explanations
This question in 9990/31 Oct/Nov 2023
Q19 · Describe what psychologists have discovered about strategies for promoting health (fear… 9990/33 Oct/Nov 2023
6 (a) Describe what psychologists have discovered about strategies for promoting health (fear arousal, Yale model of communication, providing information). [8] (b) Evaluate what psychologists have discovered about strategies for promoting health (fear arousal, Yale model of communication, providing information), including a discussion of quantitative and qualitative data. [10] Psychology and organisations Answer all questions.
18 marks
Mark scheme: 6(a) Describe what psychologists have discovered about 8 strategies for promoting health (fear arousal, Yale model of communication, providing information). Strategies for promoting health, including the following • fear arousal (Janis and Feshbach, 1953; Cowpe, 1989) • Yale model of communication • providing information (Lewin, 1992) Fear arousal – Janis and Feshbach, 1953 Independent groups design experiment using 200 High School students (mean age 15 years) each exposed to lecture and administration of questionnaire to record emotional reactions 3 times. Group 1 (50) – High Fear Arousal Group – given lecture on dental hygiene and its effects including slides showing diseased mouths and explanation of diseases including cancer and consequences. Group 2 (50) – Moderate Fear Arousal Group – given similar lecture as group one and similar picture but less disturbing. Group 3 (50) – Minimal Fear Arousal Group – Lecture about teeth and cavities, without pictures or consequences. Control group (50) – given lecture about the structure of the human eye. Questionnaire given one week before lecture, after lecture and one week after lecture to gauge emotional reaction and level of conformity. Minimal fear arousal most effective in encouraging students to adopt the oral hygiene recommendations. 6(a) Fear arousal – Cowpe, 1989 Aim was to test effectiveness of advertising campaign. Two 60 second adverts made showing the cause of chip pan fires (overfilling and inattendance). Shown in ten UK regions between 1976–1984. 12% drop in fires and high levels of awareness of the dangers of chip pan fires reported. Yale model of communication The source/the communicator – who is giving the message; are they credible, trustworthy? If a trustworthy person such as a doctor or scientist is giving the information to the person this is more likely to bring about behaviour change. The message / the communication / the context – is it clear and direct, one or two sided, vivid and colourful? If is the clear and attention-grabbing health message the person is more likely to pay attention to it (and this could then bring about change in their health behaviour). The medium – radio, TV, print, one-to-one, personal. This depends on the target audience. Health promotion aimed at young people could be best place on social media whereas older people might be better on TV or in the newspaper. The target / the audience – Who is the message aimed at? Is the audience sympathetic, knowledgeable? If the audience is not knowledgeable it is best to keep the message simple or show images (such as with a stopping smoking campaign that shows images of the damage caused by smoking). 6(a) The situation – where will the message be received, home, cinema, doctors? Where are the people most likely to be receptive to the health promotion message? Is it when they feel relaxed at home or when they are thinking about their health behaviour (e.g. at the doctor’s surgery). The candidate might also consider the stages of the process (e.g. attention, comprehension and acceptance/reaction). Providing information – Lewin, 1992 – (not 2002) 176 patients recently suffered a heart attack were randomly allocated to either 1) self-help rehab programme 2) standard care plus a placebo package of information and informal counselling. Psychological adjustments better in the rehab group at one year. Significantly less appointments with GPs and fewer readmitted to hospital in first six months. Mark according to the levels of response descriptors in Table A. Other appropriate responses should also be credited. 6(b) Evaluate what psychologists have discovered about 10 strategies for promoting health (fear arousal, Yale model of communication, providing information), including a discussion of quantitative and qualitative data. A range of issues could be used for evaluation here. These include: • Named issue – quantitative and qualitative data Quantitative data in Cowpe (percentage of decrease in chip pan fires), Quantative data collected from a variety of sources in Lewin et al. study. Quantitative in Janis and Feshbeck e.g. % of students who had changed their tooth brushing behaviour. Social desirability in the Lewin study and Janis and Feshbeck due to self-report measures used. Lack of social desirability in Cowpe as this was secondary data from government statistics of chip pan fires. Strengths and weaknesses of quantitative/qualitative data • Longitudinal research • Usefulness • Generalisability of the samples used in the studies. • Ecological validity of the studies. • Holistic nature of Yale Model of Communication • Individual vs situational explanations
This question in 9990/33 Oct/Nov 2023
Q20 · Outline one example of a sample of children used in a study of healthy eating 9990/32 Feb/March 2024
10 (a) Outline one example of a sample of children used in a study of healthy eating. [2] (b) Explain one reason why it is important to use children in psychological research on healthy eating. [2]
4 marks
Mark scheme: 10(a) Outline one example of a sample of children used in a study of healthy 2 Need to include the specific ages of the eating. children No credit to primary children, young Award 2 marks for an outline of an example of a sample of children used in a children, under age of 6. study of healthy eating. Award 1 mark for a basic outline of an example of a sample of children used in Pre-school children (1) a study of healthy eating. Likely content: Tapper et al. (2003): 26 two- to four-year-olds attending the university’s daycare nursery OR 26 children aged 5–6 years in Bangor in North Wales OR 28 children aged 5–6 years in Bangor in North Wales OR The entire primary age range (4–11 years) in three schools, in Bangor in North Wales, Harwell in Oxfordshire and Salford in Manchester OR Two schools in Lambeth in south London – age 4–11 years Credit can be given to other studies on healthy eating e.g. Silva et al. (2013): 122 Private Schools and 173 Public Schools in Brazil Example: Primary age children, 4–11 years (1) From 3 schools in the U.K. (1) Other appropriate responses should also be credited. 10(b) Explain one reason why it is important to use children in psychological 2 Context = healthy eating research on healthy eating. Award 2 marks for an outline of importance of using children in psychological research on healthy eating Award 1 mark for a basic outline of importance of using children in psychological research on healthy eating OR Award 1 mark for an outline of importance of using children in psychological research with no reference to healthy eating Likely content: • Children are less influenced by demand characteristics as they may be unaware they are in a study (or lack the understanding of what this means). • Can investigate the effects of implementing a healthy eating strategy on children and follow them up when they are older to see if this has had an impact on their eating patterns in later life. • Healthy eating strategy can be implemented in a school environment where all of the children attend and can be introduced in a similar way by the teachers at the school. Example: It is important to use children in psychological research on healthy eating so that psychologists can investigate the impact of a strategy for healthy eating implemented in schools when children are young in the long term. (1) The children can be followed-up as adults to see if the healthy eating strategy is still having an impact. (1) Other appropriate responses should also be credited.
This question in 9990/32 Feb/March 2024
Q21 · Mr Sharma is a teacher in a school who is concerned that his students are not washing… 9990/32 Feb/March 2024
11 Mr Sharma is a teacher in a school who is concerned that his students are not washing their hands correctly. (a) Suggest how Mr Sharma could use fear arousal to encourage his students to wash their hands correctly. Your answer must be ethical. [4] (b) Explain one practical problem that Mr Sharma might have with implementing what you have suggested in part (a). [2]
6 marks
Mark scheme: 11(a) Mr Sharma is a teacher in a school who is concerned that his students 4 Idea = 1 mark e.g. film, slideshow, are not washing their hands correctly. presentation – doesn’t have to be directly linked to fear arousal. Suggest how Mr Sharma could use fear arousal to encourage his 1 mark for elaboration of this idea. students to wash their hands correctly. Your answer must be ethical. Award 3–4 marks for a detailed answer with clear understanding of fear arousal linked to help Mr Sharma to encourage his students to wash their hands correctly. Award 1–2 marks for a basic answer with some understanding of fear arousal with an attempt to link to help Mr Sharma to encourage his students to wash their hands correctly. Syllabus content: • Fear arousal: use of fear to improve health, e.g. Janis and Feshbach (1953). Likely content: Use minimal fear arousal – occasionally referring to the consequences of not washing hands correctly. For example, reference to how germs are passed through poor hand washing and mild illness. Example: Mr Sharma should demonstrate to his students how to wash their hands correctly and get them to practice with him. (1) He should use minimal fear arousal in his demonstration of hand washing. (1) He could also put up a poster in the classroom/hallways that have photographs of the procedure for hand washing as well as showing how germs can spread through poor handwashing. (1) The poster could mention that colds and the flu can be passed through poor handwashing from person to person. (1) Mr Sharma’s students will feel minimal fear arousal and will be motivated to wash their hands correctly so that they do not spread germs and/or become unwell. (1) Other appropriate responses should also be credited. 11(b) Explain one practical problem that Mr Sharma might have with 2 No credit to ethics of what Mr Sharma does implementing what you have suggested in part (a). but can credit that it might lead to distress if they are unable to wash hands in the future. Award 2 marks for a detailed explanation of the practical problem in the context of implementing this suggestion with students. Award 1 mark for a basic explanation of the practical problem. Problems may include: • Students may not taking it seriously. • The habit of how the student washes their hands may be difficult to change as it is unconscious and habitual. • Students will have experienced illnesses in the past and feel they were not very serious and so will not be motivated to change how they wash their hands. Example: One practical problem of using this suggestion of minimal fear arousal with Mr Sharma’s students is that they already have a technique for cleaning their hands that they have been using for a number of years. (1) They have a habit of washing their hands in a certain way and the poster and demonstration with minimal fear will not be enough for them to break this habit. (1) Other appropriate responses should also be credited.
This question in 9990/32 Feb/March 2024
Q22 · Describe what psychologists have discovered about: • unrealistic optimism, and • positive… 9990/31 May/June 2024
12 (a) Describe what psychologists have discovered about: • unrealistic optimism, and • positive psychology. [6] (b) Evaluate what psychologists have discovered about: • unrealistic optimism, and • positive psychology, including a discussion about the idiographic versus nomothetic approach. Evaluation in your answer can include strengths, weaknesses and a discussion of issues and debates. [10] Section D: Organisational Psychology Answer all questions.
16 marks
Mark scheme: 12(a) Describe what psychologists have discovered about: unrealistic optimism, and positive psychology. Use Table A: AO1 Knowledge and understanding to mark candidate responses to this question. Candidates must discuss both features of unrealistic optimism (reason for disregarding positive health advice) and positive psychology (defining positive psychology), but they do not need to use the Weinstein or Shoshani and Steinmetz examples from the syllabus. Unrealistic optimism (reason for disregarding positive health advice) Unrealistic optimism is believing that you are less likely to experience negative health compared to other people or objective indicators that you will experience poor health. The person thinks they are more likely to experience good health or have a good outcome when they do receive a diagnosis of a condition. For example, someone who has had a heart attack will believe they are more likely to not experience one again, will recover fully after treatment, will not have to make changes to their diet and exercise to avoid the heart attack happening again in the future. part of the question even if the response otherwise meets the criteria for Level 3. Question Answer Marks Guidance 12(a) Weinstein, 1980 Two studies. Study 1 found college students rated their own changes to be above average for experiencing positive events and below average for experiencing negative events from a list of 42. Study 2 asked students to list factors they thought would influence their own chances of experiencing 8 future events. When a second group of students read it they reported less unrealistic optimism for the same 8 events. This led the researchers to conclude that the unrealistic optimism was only experienced when people focus on their own chances of achieving these outcomes and don’t realise that others may have just as many factors in their favour. Positive psychology: defining positive psychology Pleasant life – Enjoying daily pleasures in life; doing things you enjoy. For example, eating good food, doing activities you enjoy (reading, walks, sport, watching films, games, etc.). Good life – Feeling you have experienced more positive than negative things in your life. Feeling your life has been well lived. Positive connections to other people (e.g. good relationships with others, satisfying work and enjoyable activities outside of work). Meaningful life – Having a purpose in your life that is greater than oneself. Being involved in service to others (e.g. charitable work/donations, altruistic behaviour). Question Answer Marks Guidance 12(a) Shoshani and Steinmetz (2014) Aim – Our major aim in this research was to examine whether participation in the intervention program predicted better mental-health outcomes throughout the middle-school years. Participants 537 seventh – ninth-grade students participated in a 1 year intervention program and were compared to 501 students in a demographically similar control school in Israel. Method – 2-year longitudinal repeated measures design. The study assessed pre- to post-test modifications in psychological symptoms and distress and in targeted well- being factors that were promoted in the experimental but not in a wait list control condition. Measures taken Demographic information Brief Symptoms Inventory (BSI) The Rosenberg Self-Esteem Scale (RSE) The General Self-Efficacy Scale Satisfaction with Life Scale (SWLS) The Life Orientation Test-Revised (LOT-R) Question Answer Marks Guidance 12(a) Intervention group had teacher training and alongside this delivered 15 lessons to students on positive psychology including activities, discussions, film clips and stories/poems. Control Group – regular social science lessons where their discussed issues relating to adolescence but no reference made to positive psychology. Results – The findings showed significant decreases in general distress, anxiety and depression symptoms among the intervention participants, whereas symptoms in the control group increased significantly. In addition, the intervention strengthened self-esteem, self-efficacy and optimism, and reduced interpersonal sensitivity symptoms. Conclusion – Demonstrate the potential benefits of evidence-based positive-psychology interventions for promoting school-children’s mental health and point to the crucial need to make education for well-being an integral part of the school curriculum. Other appropriate responses should also be credited. Question Answer Marks Guidance 12(b) Evaluate what psychologists have discovered about: unrealistic optimism, and positive psychology, including a discussion about the idiographic versus nomothetic approach. Evaluation in your answer can include strengths, weaknesses and a discussion of issues and debates. Use Table B: AO3 Analysis and evaluation to mark candidate responses to this question. A range of issues could be used for evaluation. These include: Named issue – idiographic versus nomothetic approach Idiographic – The type of unrealistic optimism a person will experience will be individual to them. The experiences of both good and poor health as well as the types of health advice and treatments offered will be individual. The experiences of pleasant, good and meaningful life, similarly, will be individual to the person. What gives one person happiness, good relationships, meaning in life will be unique to each person. Nomothetic – Both theories do offer a general law. Unrealistic optimism is that most people have an unrealistic view of their health – that they will not experience poor health and if they do, they will have a good outcome after treatment. Positive psychology – in order to experience happiness, we must have a pleasant, good and meaningful life. 10 Question Answer Marks Guidance 12(b) Individual and situational explanations – Unrealistic optimism is mainly an individual explanation as the person is ignoring things in their situation that are indicating poor health/poor health outcomes (e.g. advice from doctors). Positive psychology is both individual (what makes a pleasant, good and meaningful life is unique to each person) and situational as factors in the situation will influence happiness. For example, the availability of charity work, fulfilling employment, leisure activities, etc. Cultural differences – Both theories are from a Western perspective. Unrealistic optimism may be due to the ready availability of good medical care which leads people to think that they will recover fully from any poor health. People living in countries where there is less access to good medical care (and they may know of people who have had poor outcomes) could lead to less of this optimism. Similarly, positive psychology is Western/affluent countries where there are more opportunities for leisure activities and charitable work. In some countries, most people may need to spend their time earning enough to support their daily basic living needs and have little opportunity for leisure, charity, etc. Psychometrics – e.g. Weinstein’s 42 life events Strengths – quantitative data so comparisons can be made; objective data; reliable. Weaknesses – lacks qualitative data/not in-depth, self-report so can be open to demand characteristics/social desirability. Generalisations from findings – Weinstein used college students from Rutgers University, New Jersey USA. This university attracts a diverse group of students. Study 2 had 120 female students from Rutgers who were doing an introductory course in psychology. Question Answer Marks Guidance 12(b) Additional issues/debates candidates may include: Application to everyday life Evaluation of quantitative data Evaluation of self-reports used Reliability Validity Reductionism versus holism Other appropriate responses should also be credited.
This question in 9990/31 May/June 2024
Q23 · Describe what psychologists have discovered about: • unrealistic optimism, and • positive… 9990/33 May/June 2024
12 (a) Describe what psychologists have discovered about: • unrealistic optimism, and • positive psychology. [6] (b) Evaluate what psychologists have discovered about: • unrealistic optimism, and • positive psychology, including a discussion about the idiographic versus nomothetic approach. Evaluation in your answer can include strengths, weaknesses and a discussion of issues and debates. [10] Section D: Organisational Psychology Answer all questions.
16 marks
Mark scheme: 12(a) Describe what psychologists have discovered about: unrealistic optimism, and positive psychology. Use Table A: AO1 Knowledge and understanding to mark candidate responses to this question. Candidates must discuss both features of unrealistic optimism (reason for disregarding positive health advice) and positive psychology (defining positive psychology), but they do not need to use the Weinstein or Shoshani and Steinmetz examples from the syllabus. Unrealistic optimism (reason for disregarding positive health advice) Unrealistic optimism is believing that you are less likely to experience negative health compared to other people or objective indicators that you will experience poor health. The person thinks they are more likely to experience good health or have a good outcome when they do receive a diagnosis of a condition. For example, someone who has had a heart attack will believe they are more likely to not experience one again, will recover fully after treatment, will not have to make changes to their diet and exercise to avoid the heart attack happening again in the future. part of the question even if the response otherwise meets the criteria for Level 3. Question Answer Marks Guidance 12(a) Weinstein, 1980 Two studies. Study 1 found college students rated their own changes to be above average for experiencing positive events and below average for experiencing negative events from a list of 42. Study 2 asked students to list factors they thought would influence their own chances of experiencing 8 future events. When a second group of students read it they reported less unrealistic optimism for the same 8 events. This led the researchers to conclude that the unrealistic optimism was only experienced when people focus on their own chances of achieving these outcomes and don’t realise that others may have just as many factors in their favour. Positive psychology: defining positive psychology Pleasant life – Enjoying daily pleasures in life; doing things you enjoy. For example, eating good food, doing activities you enjoy (reading, walks, sport, watching films, games, etc.). Good life – Feeling you have experienced more positive than negative things in your life. Feeling your life has been well lived. Positive connections to other people (e.g. good relationships with others, satisfying work and enjoyable activities outside of work). Meaningful life – Having a purpose in your life that is greater than oneself. Being involved in service to others (e.g. charitable work/donations, altruistic behaviour). Question Answer Marks Guidance 12(a) Shoshani and Steinmetz (2014) Aim – Our major aim in this research was to examine whether participation in the intervention program predicted better mental-health outcomes throughout the middle-school years. Participants 537 seventh – ninth-grade students participated in a 1 year intervention program and were compared to 501 students in a demographically similar control school in Israel. Method – 2-year longitudinal repeated measures design. The study assessed pre- to post-test modifications in psychological symptoms and distress and in targeted well- being factors that were promoted in the experimental but not in a wait list control condition. Measures taken Demographic information Brief Symptoms Inventory (BSI) The Rosenberg Self-Esteem Scale (RSE) The General Self-Efficacy Scale Satisfaction with Life Scale (SWLS) The Life Orientation Test-Revised (LOT-R) Question Answer Marks Guidance 12(a) Intervention group had teacher training and alongside this delivered 15 lessons to students on positive psychology including activities, discussions, film clips and stories/poems. Control Group – regular social science lessons where their discussed issues relating to adolescence but no reference made to positive psychology. Results – The findings showed significant decreases in general distress, anxiety and depression symptoms among the intervention participants, whereas symptoms in the control group increased significantly. In addition, the intervention strengthened self-esteem, self-efficacy and optimism, and reduced interpersonal sensitivity symptoms. Conclusion – Demonstrate the potential benefits of evidence-based positive-psychology interventions for promoting school-children’s mental health and point to the crucial need to make education for well-being an integral part of the school curriculum. Other appropriate responses should also be credited. Question Answer Marks Guidance 12(b) Evaluate what psychologists have discovered about: unrealistic optimism, and positive psychology, including a discussion about the idiographic versus nomothetic approach. Evaluation in your answer can include strengths, weaknesses and a discussion of issues and debates. Use Table B: AO3 Analysis and evaluation to mark candidate responses to this question. A range of issues could be used for evaluation. These include: Named issue – idiographic versus nomothetic approach Idiographic – The type of unrealistic optimism a person will experience will be individual to them. The experiences of both good and poor health as well as the types of health advice and treatments offered will be individual. The experiences of pleasant, good and meaningful life, similarly, will be individual to the person. What gives one person happiness, good relationships, meaning in life will be unique to each person. Nomothetic – Both theories do offer a general law. Unrealistic optimism is that most people have an unrealistic view of their health – that they will not experience poor health and if they do, they will have a good outcome after treatment. Positive psychology – in order to experience happiness, we must have a pleasant, good and meaningful life. 10 Question Answer Marks Guidance 12(b) Individual and situational explanations – Unrealistic optimism is mainly an individual explanation as the person is ignoring things in their situation that are indicating poor health/poor health outcomes (e.g. advice from doctors). Positive psychology is both individual (what makes a pleasant, good and meaningful life is unique to each person) and situational as factors in the situation will influence happiness. For example, the availability of charity work, fulfilling employment, leisure activities, etc. Cultural differences – Both theories are from a Western perspective. Unrealistic optimism may be due to the ready availability of good medical care which leads people to think that they will recover fully from any poor health. People living in countries where there is less access to good medical care (and they may know of people who have had poor outcomes) could lead to less of this optimism. Similarly, positive psychology is Western/affluent countries where there are more opportunities for leisure activities and charitable work. In some countries, most people may need to spend their time earning enough to support their daily basic living needs and have little opportunity for leisure, charity, etc. Psychometrics – e.g. Weinstein’s 42 life events Strengths – quantitative data so comparisons can be made; objective data; reliable. Weaknesses – lacks qualitative data/not in-depth, self-report so can be open to demand characteristics/social desirability. Generalisations from findings – Weinstein used college students from Rutgers University, New Jersey USA. This university attracts a diverse group of students. Study 2 had 120 female students from Rutgers who were doing an introductory course in psychology. Question Answer Marks Guidance 12(b) Additional issues/debates candidates may include: Application to everyday life Evaluation of quantitative data Evaluation of self-reports used Reliability Validity Reductionism versus holism Other appropriate responses should also be credited.
This question in 9990/33 May/June 2024
Q24 · A teacher sees one class of 11-year-olds eating too much unhealthy food 9990/31 Oct/Nov 2024
9 A teacher sees one class of 11-year-olds eating too much unhealthy food. She wants to promote healthy eating. Suggest how the teacher could decrease the amount of unhealthy food eaten by the children in this class. [4]
4 marks
Mark scheme: 9 A teacher sees one class of 11-year-olds eating too much unhealthy food. She 4 Cap at 3 if not specific to one wants to promote healthy eating. class. Suggest how the teacher could decrease the amount of unhealthy food eaten by Cap at 3 if not referencing the children in this class. reducing amount of unhealthy food Award 3–4 marks for a detailed answer with clear understanding of how to decrease the amount of unhealthy food eaten by the children Should be suitable for 11 year Award 1–2 marks for a basic answer with some understanding of how to how to olds – cap at 3 if it is something decrease the amount of unhealthy food eaten by the children that could also be done with adults. Syllabus content: If it is very unsuitable (e.g. very Health promotion in schools with a focus on healthy eating, including a study, e.g., unethical) – do not credit these Tapper et al. (2003) ideas. Suggestions could include Using the same techniques • Use of a reward system for fewer unhealthy foods eaten e.g., sticker chart, used by Tapper et al. cap at 3 certificate for certain number of stickers (as this study did not try to • Promotion of healthy foods as an alternative e.g. making more healthy food options reduce the amount of unhealthy in the school canteen and/or fewer unhealthy foods food eaten). • Using information leaflets and/or films to educate children as to the health problems Can give full marks if the associated with unhealthy eating response then extends the • Introduction of cooking classes that promote healthier cooking e.g. using less fat in suggestion to include reducing cooking, more vegetables unhealthy food eaten. • Asking children to keep a diary of the foods they eat at home to promote awareness of unhealthy foods eaten Candidates could make one very detailed suggestion or a number of others in less detail. However, it must be coherent for full marks and clear that it is for the same children if there is more than one suggestion. 9 Example: The teacher could introduce a competition for the class to find as many ways as possible to make commonly eaten foods/meals healthier. (1) The parents of the children could be involved with the teacher writing to them saying how important healthy eating is and that she would like them to be involved in promoting healthy eating at home. (1) Children could then pick food items/meals and substitute unhealthy foods for healthy alternatives e.g., vegetables instead of fries or curry without cream. (1) Record of each of these suggestions kept for each child and the one with the most healthy changes receives a prize e.g. book token or certificate awarded for 5/10/15 suggestions. (1) All suggestions made into a leaflet that could be used with all members of the school and their parents. (1) Other appropriate responses should also be credited.
This question in 9990/31 Oct/Nov 2024
Q25 · A teacher sees one class of 11-year-olds eating too much unhealthy food 9990/33 Oct/Nov 2024
9 A teacher sees one class of 11-year-olds eating too much unhealthy food. She wants to promote healthy eating. Suggest how the teacher could decrease the amount of unhealthy food eaten by the children in this class. [4]
4 marks
Mark scheme: 9 A teacher sees one class of 11-year-olds eating too much unhealthy food. She 4 Cap at 3 if not specific to one wants to promote healthy eating. class. Suggest how the teacher could decrease the amount of unhealthy food eaten by Cap at 3 if not referencing the children in this class. reducing amount of unhealthy food Award 3–4 marks for a detailed answer with clear understanding of how to decrease the amount of unhealthy food eaten by the children Should be suitable for 11 year Award 1–2 marks for a basic answer with some understanding of how to how to olds – cap at 3 if it is something decrease the amount of unhealthy food eaten by the children that could also be done with adults. Syllabus content: If it is very unsuitable (e.g. very Health promotion in schools with a focus on healthy eating, including a study, e.g., unethical) – do not credit these Tapper et al. (2003) ideas. Suggestions could include Using the same techniques • Use of a reward system for fewer unhealthy foods eaten e.g., sticker chart, used by Tapper et al. cap at 3 certificate for certain number of stickers (as this study did not try to • Promotion of healthy foods as an alternative e.g. making more healthy food options reduce the amount of unhealthy in the school canteen and/or fewer unhealthy foods food eaten). • Using information leaflets and/or films to educate children as to the health problems Can give full marks if the associated with unhealthy eating response then extends the • Introduction of cooking classes that promote healthier cooking e.g. using less fat in suggestion to include reducing cooking, more vegetables unhealthy food eaten. • Asking children to keep a diary of the foods they eat at home to promote awareness of unhealthy foods eaten Candidates could make one very detailed suggestion or a number of others in less detail. However, it must be coherent for full marks and clear that it is for the same children if there is more than one suggestion. 9 Example: The teacher could introduce a competition for the class to find as many ways as possible to make commonly eaten foods/meals healthier. (1) The parents of the children could be involved with the teacher writing to them saying how important healthy eating is and that she would like them to be involved in promoting healthy eating at home. (1) Children could then pick food items/meals and substitute unhealthy foods for healthy alternatives e.g., vegetables instead of fries or curry without cream. (1) Record of each of these suggestions kept for each child and the one with the most healthy changes receives a prize e.g. book token or certificate awarded for 5/10/15 suggestions. (1) All suggestions made into a leaflet that could be used with all members of the school and their parents. (1) Other appropriate responses should also be credited.
This question in 9990/33 Oct/Nov 2024
Q26 · Dr Singh wants to encourage his patients to exercise regularly and runs a clinic to… 9990/32 Feb/March 2025
11 Dr Singh wants to encourage his patients to exercise regularly and runs a clinic to support them to attend swimming or running classes. (a) Suggest how Dr Singh could use contracts to improve the adherence of his patients to regular exercise. [4] (b) For your suggestion in part (a): Explain one practical problem with implementing your suggestion. [2]
6 marks
Mark scheme: 11 Dr Singh wants to encourage his patients to exercise regularly and runs a clinic to support them to attend swimming or running classes. 11(a) Suggest how Dr Singh could use contracts to improve the adherence of his 4 Credit can be given to one or patients to regular exercise. more suggestions. Award 3–4 marks for a detailed answer with clear understanding of using contracts to 3–4 marks must link to contract improve adherence to Dr Singh’s exercise regime. for exercise. Award 1–2 marks for a basic answer with some understanding of using contracts to improve adherence to Dr Singh’s exercise regime. 4 marks – in addition to the contract must include the follow Syllabus content: up to check adherence • Individual behavioural techniques: contracts Can credit a small reward that is Example: appropriate to a doctor (e.g. Dr Singh can use a contract with his patients to get them to attend swimming/running complete 10 classes and get 2 classes by reviewing their current exercise level with them. (1) He/she can then have free) them agree to attend at least one class per week and plan out when they will do this. (1) The patient will sign the contract agreeing to attend this class. (1) The patient will return to the exercise clinic every two weeks to review their progress with Dr Singh. (1) Other appropriate responses should also be credited. 11(b) For your suggestion in part (a): 2 Explain one practical problem with implementing your suggestion. No credit for giving a solution. Award 2 marks for a detailed explanation of one practical problem in the context of No credit for stating that some implementing this suggestion with patients. patients will not sign the Award 1 mark for a basic explanation/identification of the practical problem. contract. Practical problems may include: • The patient may say they are attending the class when they are not. • The patient may be attending but put in no effort during the class so are not benefitting from the exercise. • Dr Singh may find it difficult to monitor a lot of patients at a time due to his time constraints. • Patients do not attend follow up appointments. Example: One practical problem could be that the patient says they are attending the class when they are not. (1) Therefore, Dr Singh cannot help them to follow their contract as he does not know what they are doing OR the patient won’t experience an improvement in their health/fitness. (1) Other appropriate responses should also be credited.
This question in 9990/32 Feb/March 2025
Q27 · Describe: • a study using fear arousal to improve health, and • a study about providing… 9990/32 Feb/March 2025
12 (a) Describe: • a study using fear arousal to improve health, and • a study about providing information so people know how to improve their health. [6] (b) Evaluate: • a study using fear arousal to improve health, and • a study about providing information so people know how to improve their health, including a discussion about longitudinal studies. Evaluation in your answer can include strengths, weaknesses and a discussion of issues and debates. [10] Section D: Organisational Psychology Answer all questions.
16 marks
Mark scheme: 12(a) Describe: 6 Award up to 4 marks where the • a study using fear arousal to improve health, and response has described only • a study about providing information so people know how to improve their part of the question even if the health. response otherwise meets the criteria for level 3. Use Table A: AO1 Knowledge and understanding to mark candidate responses to this Tapper and Fox et al. can be question. credited to ‘providing information. Candidates must describe a study on fear arousal and providing information, but they do not need to use the Janis and Feshbach or the Lewin et al. examples from the syllabus. Answers may include: Syllabus content: • fear arousal: use of fear to improve health, including a study, e.g. Janis and Feshbach (1953) • providing information: giving information so people know how to improve their health, including a study, e.g. Lewin et al. (1992). Fear arousal – Janis and Feshbach, 1953 Independent groups design experiment using 200 High School students (mean age 15 years) each exposed to lecture and administration of questionnaire to record emotional reactions 3 times. Group 1 (50) – High Fear Arousal Group – given lecture on dental hygiene and its effects including slides showing diseased mouths and explanation of diseases including cancer and consequences. Group 2 (50) – Moderate Fear Arousal Group – given similar lecture as group one and similar picture but less disturbing. Group 3 (50) – Minimal Fear Arousal Group – lecture about teeth and cavities, without pictures or consequences. Control group (50) – given lecture about the structure of the human eye. 12(a) Questionnaire given one week before lecture, after lecture and one week after lecture to gauge emotional reaction and level of conformity. Minimal fear arousal most effective in encouraging students to adopt the oral hygiene recommendations. OR Fear arousal – Cowpe, 1989 Aim was to test effectiveness of advertising campaign. 60 second adverts shown on television, Showed the initial causes of the fire (overfilling and inattendance), then showed the actions required to put the chip pan fire out e.g. turn off the heat, cover the pan with a damp cloth or leave the pan to cool down. Shown on ten regional television areas in UK from 1976–1984. 12% drop in fires and high levels of awareness of the dangers of chip pan fires reported. Providing information: giving information so people know how to improve their health Lewin, 1992 176 patients recently suffered a heart attack were randomly allocated to either: 1) self-help rehab programme 2) standard care plus a placebo package of information and informal counselling. Psychological adjustment was assessed by the Hospital Anxiety and Depression Scale and 30 item General Health Questionnaire (also a measure of psychological status) used on all participants. These assessments were done at 6 weeks, 6 months and 12 months post discharge. At 6 and 12 months post discharge general practitioner asked about number of contacts with patient and whether patient had been admitted to hospital in the preceding 6 months. After discharge the facilitator made contact with both groups of patients at 1,3, and 6 weeks. In the case of the rehabilitation group she checked the patient’s progress with the programme, encouraged compliance with the exercises in the manual, and helped to solve any problems with the manual. 12(a) Psychology adjustments better in the rehabilitation group at 1 year. They also had significantly less contact with their general practitioners during the following year and significantly fewer were readmitted to hospital in the first 6 months. The improvement was greatest among patients who were clinically anxious or depressed at discharge from hospital. Other appropriate responses should also be credited. 12(b) Evaluate: 10 Credit evaluation of Tapper et • a study using fear arousal to improve health, and al. and Fox et al. • a study about providing information so people know how to improve their health, including a discussion about longitudinal studies. Evaluation in your answer can include strengths, weaknesses and a discussion of issues and debates. Use Table B: AO3 Analysis and evaluation to mark candidate responses to this question. A range of issues could be used for evaluation. These include: • Named issue – longitudinal studies- Strengths include that it shows change in behaviour over time, often can get more detail due to the length of time spent with participants. Weaknesses include that it involves a lot of commitment/time/cost of the psychologist and their university/funding body and participant attrition. Cowpe study took place over from 1976–1984. Lewin 1992 – over 12 months. Likely to argue that Janis and Feshbeck is snapshot as just over a week so cannot measure long term changes in behaviour. • Objective and subjective data - Janis and Feshbeck can be considered to be objective as the results are quantitative so not interpreted by the researcher. However, can be considered to be subjective as there could be social desirability and participants said they had changed tooth brushing behaviour, when they had not. Quantitative data in Cowpe (percentage of decrease in chip pan fires) is objective as government statistics. Lewin’s study – objective data from doctors regarding frequency of visits and hospital admission. Subjective data from psychological measures used. 12(b) • Individual and situational explanations – Cowpe, Lewin and Janis and Feshbeck are situational as they concluded it is the adverts (Cowpe) or the Angina plan (Lewin) or the type of fear arousal used (Janis and Feshbeck) that led to the behaviour change. Likely to mention individual explanations that could have affected behaviour such as health of patient (Lewin), whether advert was seen/paid attention to (Cowpe) and motivation to change tooth brushing behaviour (Janis and Feshbeck) • Cultural differences – Can argue that these techniques could work cross-culturally as everyone experiences these health concerns (oral health, angina, risk of fire). Could also argue that there may be cultural differences in how a different culture might respond to fear arousal and/or providing information. Some cultures might not respond well to a self-help programme and require the intervention of their practitioner. • Ethics – Psychological harm to the participants in the Janis and Feshbeck study exposed to high fear arousal. No mention made of consent in the study (participants were 15). Cowpe – no consent required as the advertisements were shown as part of a government campaign and data collected from government statistics. Consent obtained in Lewin study and no harm caused. Could argue that the self -help programme was not offered to control group after the study. Other issues could include: • evaluation of quantitative data • evaluation of self-reports used • evaluation of experiments • reliability • generalisations from findings • validity/ecological validity Other appropriate responses should also be credited. Section D: Organisational Psychology
This question in 9990/32 Feb/March 2025
Q28 · Describe: • a study on promoting healthy eating in schools, and • a study on promoting… 9990/32 May/June 2025
12 (a) Describe: • a study on promoting healthy eating in schools, and • a study on promoting health and safety in worksites. [6] (b) Evaluate: • a study on promoting healthy eating in schools, and • a study on promoting health and safety in worksites, including a discussion about experiments. Evaluation in your answer can include strengths, weaknesses and a discussion of issues and debates. [10] Section D: Organisational Psychology Answer all questions.
16 marks
Mark scheme: 12(a) Describe: 6 Award up to 4 marks • a study on promoting healthy eating in schools, and where the response has • a study on promoting health and safety in worksites. described only part of the question even if the Use Table A: AO1 Knowledge and understanding to mark candidate responses to this response otherwise meets question. the criteria for level 3. Candidates must discuss both types of a study on healthy eating in schools and a study on health and safety in worksites. They can include examples of any appropriate studies. For L3 for a study need some detail of the Details may include: procedure (e.g. details of how food dudes was used Study on healthy eating in schools with children or the participants; details of how Tapper et al. token economy carried Food dudes. – a number of different studies that were completed by the authors are described out) and at least 1 result. in the study and any or all are creditworthy. Whole school programme of 4–11 year olds in a primary school. Shown food dudes Alternative study on programmes and given a course of lesson materials including stickers, letters home pack, staff healthy eating in manual, etc. Lasted for 16 days and was covered each day in school. Children were schools – O’Brien et al. enthusiastic about the work and improved their attendance. After four months reported to (2021) Abstract continue to be eating more fruit and vegetables. Schools are identified as a key setting to influence Study on health and safety in worksites children's and adolescents' healthy Fox et al. eating. This umbrella Workers at two open-pit mines used as participants. Employees earned stamps for working review synthesised without lost-time injuries, not being involved in equipment damaging accidents, adopting evidence from systematic safety suggestions and behaviour which prevent injury/accident. Lost stamps if they/other reviews of school-based workers injured, caused equipment damage or failed to report injury/accident. Stamps could nutrition interventions be exchanged for thousands of items in a shop on site. Results – large reduction in lost days designed to improve due to injuries, lost time injuries and costs of accidents/injuries. Reduction in costs far exceed dietary intake outcomes in the cost of token economy and improvements maintained over several years. children aged 6 to 18 years. Other appropriate responses should also be credited. 12(a) They undertook a systematic search of six electronic databases and grey literature to identify relevant reviews of randomized controlled trials. The review findings were categorised for synthesis by intervention type according to the World Health Organisation Health Promoting Schools (HPS) framework domains: nutrition education; food environment; all three HPS framework domains; or other (not aligned to HPS framework domain). Thirteen systematic reviews were included. Overall, the findings suggest that school-based nutrition interventions, including nutrition education, food environment, those based on all three domains of the HPS framework, and eHealth interventions, can have a positive effect on some dietary outcomes, including fruit, fruit and vegetables combined, and fat intake. 12(a) These results should be interpreted with caution, however, as the quality of the reviews was poor. Though these results support continued public health investment in school-based nutrition interventions to improve child dietary intake, the limitations of this umbrella review also highlight the need for a comprehensive and high quality systematic review of primary studies. Alternative study on health and safety at worksites. LaMontagne et al. (2004Aims: (1) To develop a transparent and broadly applicable method for assessing occupational safety and health (OSH) programmes or management systems; (2) to assess OSH programmes in a sample of manufacturing worksites; and (3) to determine whether a management focused occupational health intervention results in 12(a) greater improvement in OSH programmes compared to minimal intervention controls. Methods: OSH programmes were assessed using an adaptation of the US Occupational Safety & Health Administration’s 1995 Program Evaluation Profile. Scores were generated from 91 binary indicator variables grouped under four “Essential Elements”. Essential Element scores were weighted to contribute to an overall programme score on a 100-point scale. Seventeen large manufacturing worksites were assessed at baseline; 15 sites completed the 16-month intervention and follow up assessments. Results: There was considerable variation in Essential Element scores across sites at baseline as judged by our instrument, particularly in 12(a) “management commitment and employee participation” and “workplace analysis”. Most sites scored highly on “hazard prevention and control” and “training and education”. For overall OSH programme scores, most sites scored in the 60–80% range at baseline, with four sites scoring below 60%, suggesting weak programmes. Intervention sites showed greater improvements than controls in the four programme elements and in overall programme scores, with significantly greater improvements in “management commitment and employee participation”. Conclusions: The OSH programme assessment method used is broadly applicable to manufacturing work settings, and baseline profiles suggest needs for improvement in OSH programmes in most such worksites. 12(a) Despite a small sample size, results showed that sustained management focused intervention can result in improvement in these OSH programme measures 12(b) Evaluate: 10 • a study on promoting healthy eating in schools, and • a study on promoting health and safety in worksites, including a discussion about experiments. Evaluation in your answer can include strengths, weaknesses and a discussion of issues and debates. Use Table B: AO3 Analysis and evaluation to mark candidate responses to this question. A range of issues could be used for evaluation. These include: • Named issue – Experiments – Likely evaluation points include – ecological validity, reliability, demand characteristics, controls, control of extraneous variables. Tapper’ study was a field study and Fox et al. was quasi experiment. • Use of children in research – Strengths – can be ethical if consent gained from parents and child can be informed of the nature of the study if old enough to understand, as improving healthy eating this will have a good outcome for the children (unless in a control group), children may not show demand characteristics if they don’t know or understand that they are in a study, children’s eating is different in different cultures due to socialisation and differences in availability/advertising of products so may not be generalisable. Weaknesses – could be ethical issues as children are more sensitive than adults, child may try and please the researcher/their teacher and this leads to demand characteristics/social desirability, children may not realise the importance of being honest about their eating outside of the classroom. • Longitudinal studies – Strengths include that it shows change in behaviour over time, often can get more detail due to the length of time spent with participants. Weaknesses include that it involves a lot of commitment/time/cost of the psychologist and their university/funding body and participant attrition. Tapper’s whole school programme was initially done over 16 days and a 4-month follow-up (at some of the schools involved). Food dudes in the nursery had a 15-month follow-up. Interventions of introducing new fruits and vegetables was done slowly which helped to increase consumption so is a strength of the longitudinal method for this research. Fox et al. 1970–1985 – 15 years. 12(b) • Generalisations from findings – Fox et al. was just done on mine workers in the USA, Tapper was on children aged 4–11 in the UK. • Quantitative and qualitative data – Likely evaluation points – depth of data, bias in interpretation of data, comparisons/statistical analysis Other issues could include: • evaluation of data collection methods used • ethics • Idiographic and nomothetic • Determinism versus free-will Other appropriate responses should also be credited. Section D: Organisational Psychology
This question in 9990/32 May/June 2025
Q29 · Outline what is meant by the debate between individual and situational explanations 9990/31 Oct/Nov 2025
10 (a) Outline what is meant by the debate between individual and situational explanations. [2] (b) Explain why one strategy for improving health has a situational explanation. [2]
4 marks
Mark scheme: 10(a) Outline what is meant by the debate between individual and situational explanations. 2 Do not credit definitions that simply use the words 1 mark – definition of individual explanation individual or situations 1 mark – definition of situational explanation Annotate with ticks to show where marks awarded An individual explanation suggests that behaviour is due to internal/dispositional factors. A situational explanation suggests that behaviour is due to environmental or external factors. The debate is about the extent to which behaviour is individual or situational. Example: The extent to which behaviour is due to internal i.e., individual factors as opposed to external/environmental i.e., situational factors (2) Individual factors are those that are internal such as their personality, but situational factors include external sources such as reinforcement (1). The debate looks at how far behaviour is affected by internal as opposed to external factors (1). How much people are affected by their individual make-up or their situation (1). 10(b) Explain why one strategy for improving health has a situational explanation. 2 Allow examples from improving health such as Strategies named in the syllabus: token economy and healthy Fear arousal and providing information eating programs like Tapper. 1 mark – outline of a health strategy Identification of health 1 mark – why that health strategy is situational strategy on its own = 0. Annotate with ticks to show where marks awarded Exercise is creditworthy. Reasons could include: External source is a situational factor and assumes all individuals react in a similar way. External source or reinforcement is not under the control of the individual. External sources do not depend on the personality or disposition. Example: The use of photographs of those with mouth cancers on cigarette packaging is used as fear arousal (1), which is a situational way to prevent someone smoking (1). This method assumes that all individuals will react in a similar way, which is why it is not individual (1). If people are provided with information in the form of pamphlets for how to improve their health this is situational (1) as the individual is not in control of the content of that leaflet and as a result can only use individual factors to choose to ignore or accept the information (1). Everyone receiving the information has received the same external material (1). Other appropriate responses should also be credited.
This question in 9990/31 Oct/Nov 2025
Q30 · Outline what is meant by the debate between individual and situational explanations 9990/33 Oct/Nov 2025
10 (a) Outline what is meant by the debate between individual and situational explanations. [2] (b) Explain why one strategy for improving health has a situational explanation. [2]
4 marks
Mark scheme: 10(a) Outline what is meant by the debate between individual and situational explanations. 2 Do not credit definitions that simply use the words 1 mark – definition of individual explanation individual or situations 1 mark – definition of situational explanation Annotate with ticks to show where marks awarded An individual explanation suggests that behaviour is due to internal/dispositional factors. A situational explanation suggests that behaviour is due to environmental or external factors. The debate is about the extent to which behaviour is individual or situational. Example: The extent to which behaviour is due to internal i.e., individual factors as opposed to external/environmental i.e., situational factors (2) Individual factors are those that are internal such as their personality, but situational factors include external sources such as reinforcement (1). The debate looks at how far behaviour is affected by internal as opposed to external factors (1). How much people are affected by their individual make-up or their situation (1). 10(b) Explain why one strategy for improving health has a situational explanation. 2 Allow examples from improving health such as Strategies named in the syllabus: token economy and healthy Fear arousal and providing information eating programs like Tapper. 1 mark – outline of a health strategy Identification of health 1 mark – why that health strategy is situational strategy on its own = 0. Annotate with ticks to show where marks awarded Exercise is creditworthy. Reasons could include: External source is a situational factor and assumes all individuals react in a similar way. External source or reinforcement is not under the control of the individual. External sources do not depend on the personality or disposition. Example: The use of photographs of those with mouth cancers on cigarette packaging is used as fear arousal (1), which is a situational way to prevent someone smoking (1). This method assumes that all individuals will react in a similar way, which is why it is not individual (1). If people are provided with information in the form of pamphlets for how to improve their health this is situational (1) as the individual is not in control of the content of that leaflet and as a result can only use individual factors to choose to ignore or accept the information (1). Everyone receiving the information has received the same external material (1). Other appropriate responses should also be credited.
This question in 9990/33 Oct/Nov 2025




 1 / 7




 2 / 7




 3 / 7




 4 / 7



 5 / 7



 6 / 7

 7 / 7
 18
 12
 12
 12
 12
 12
 12
 18
 12
 12
 12
 18
 12
 12
 18
 12
 12
 18
 18
 4
 6
 16
 16
 4
 4
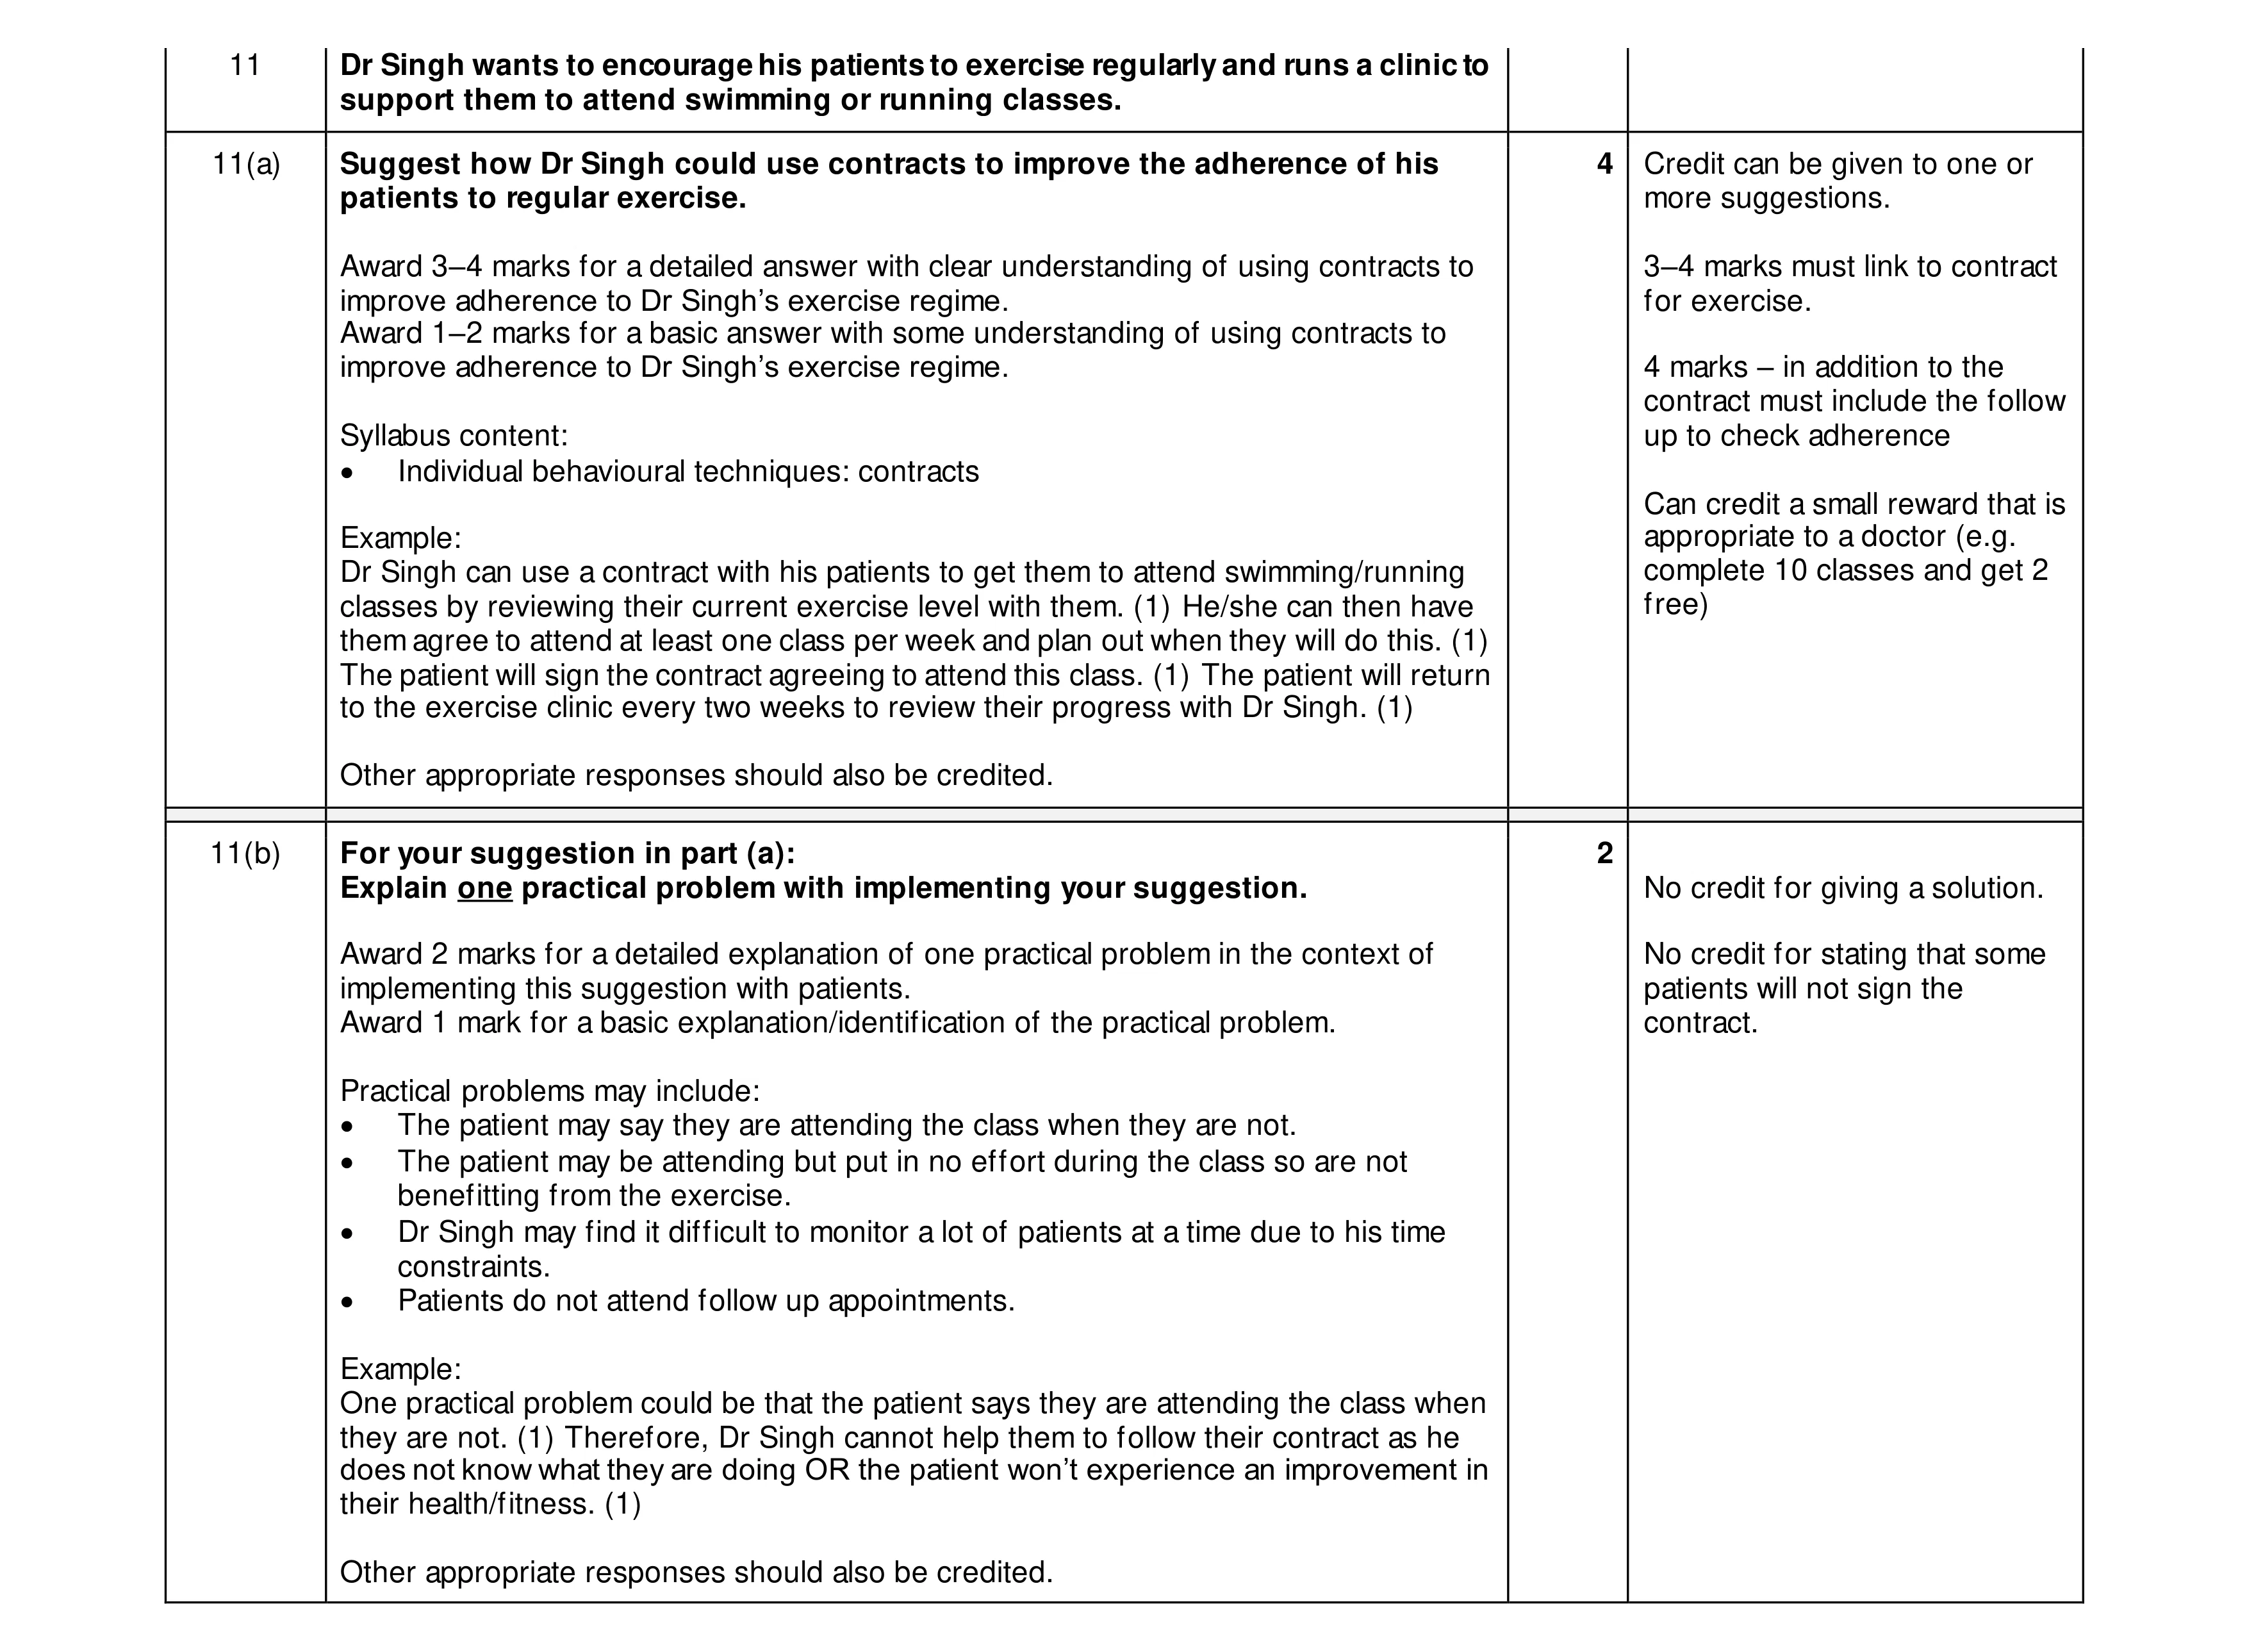 6
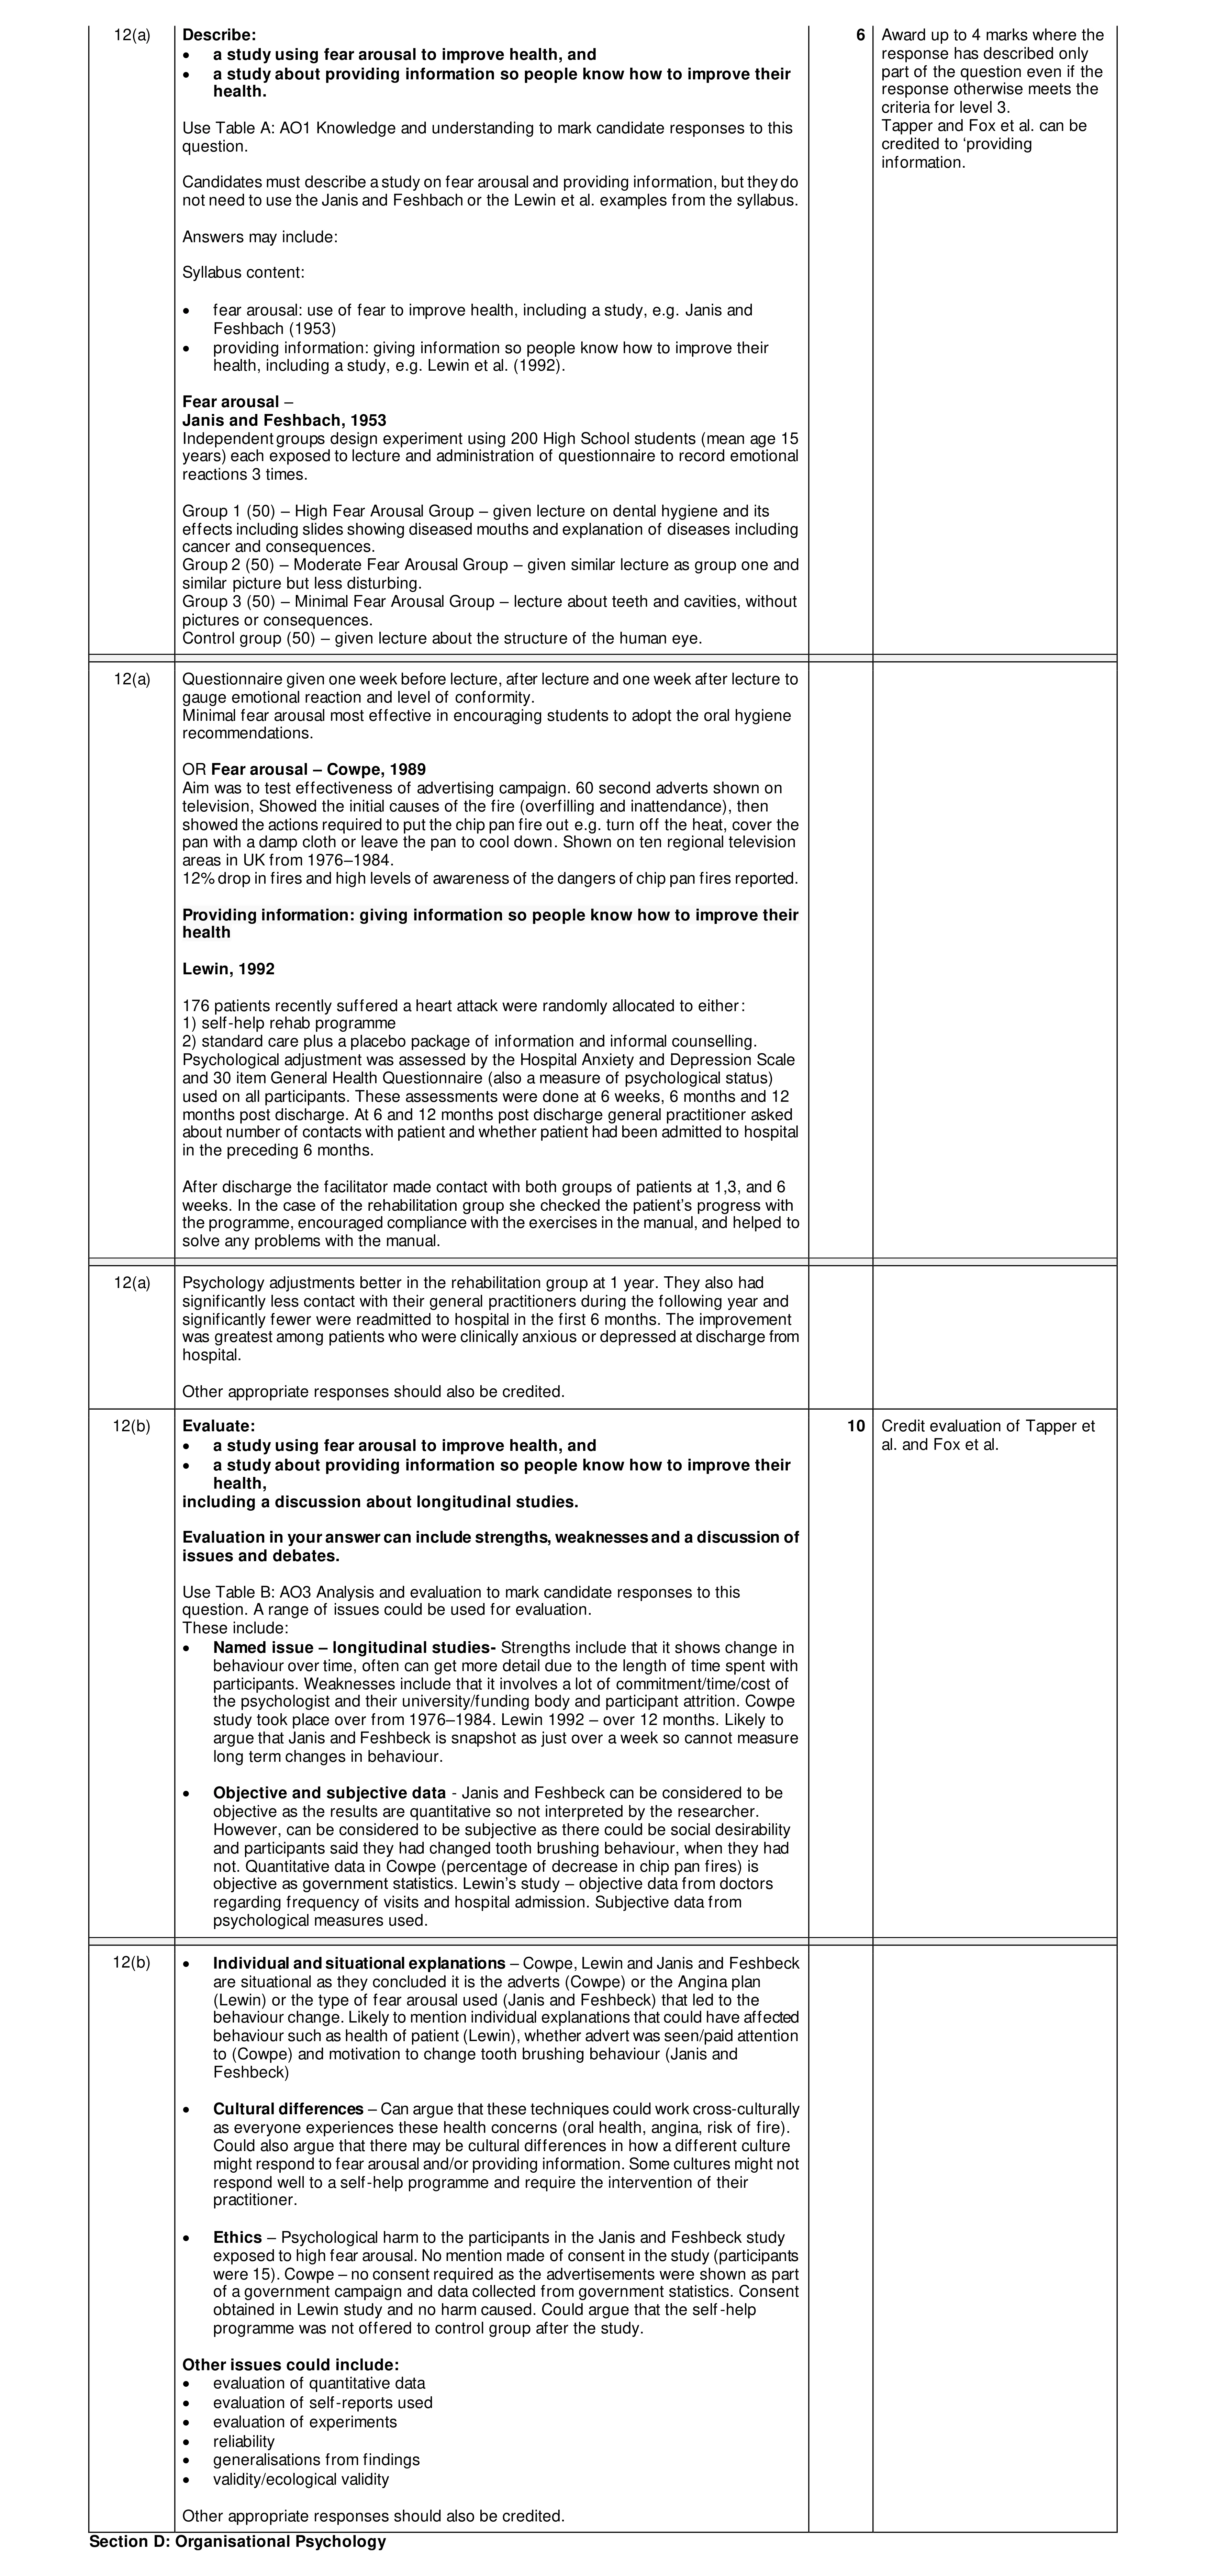 16
 16
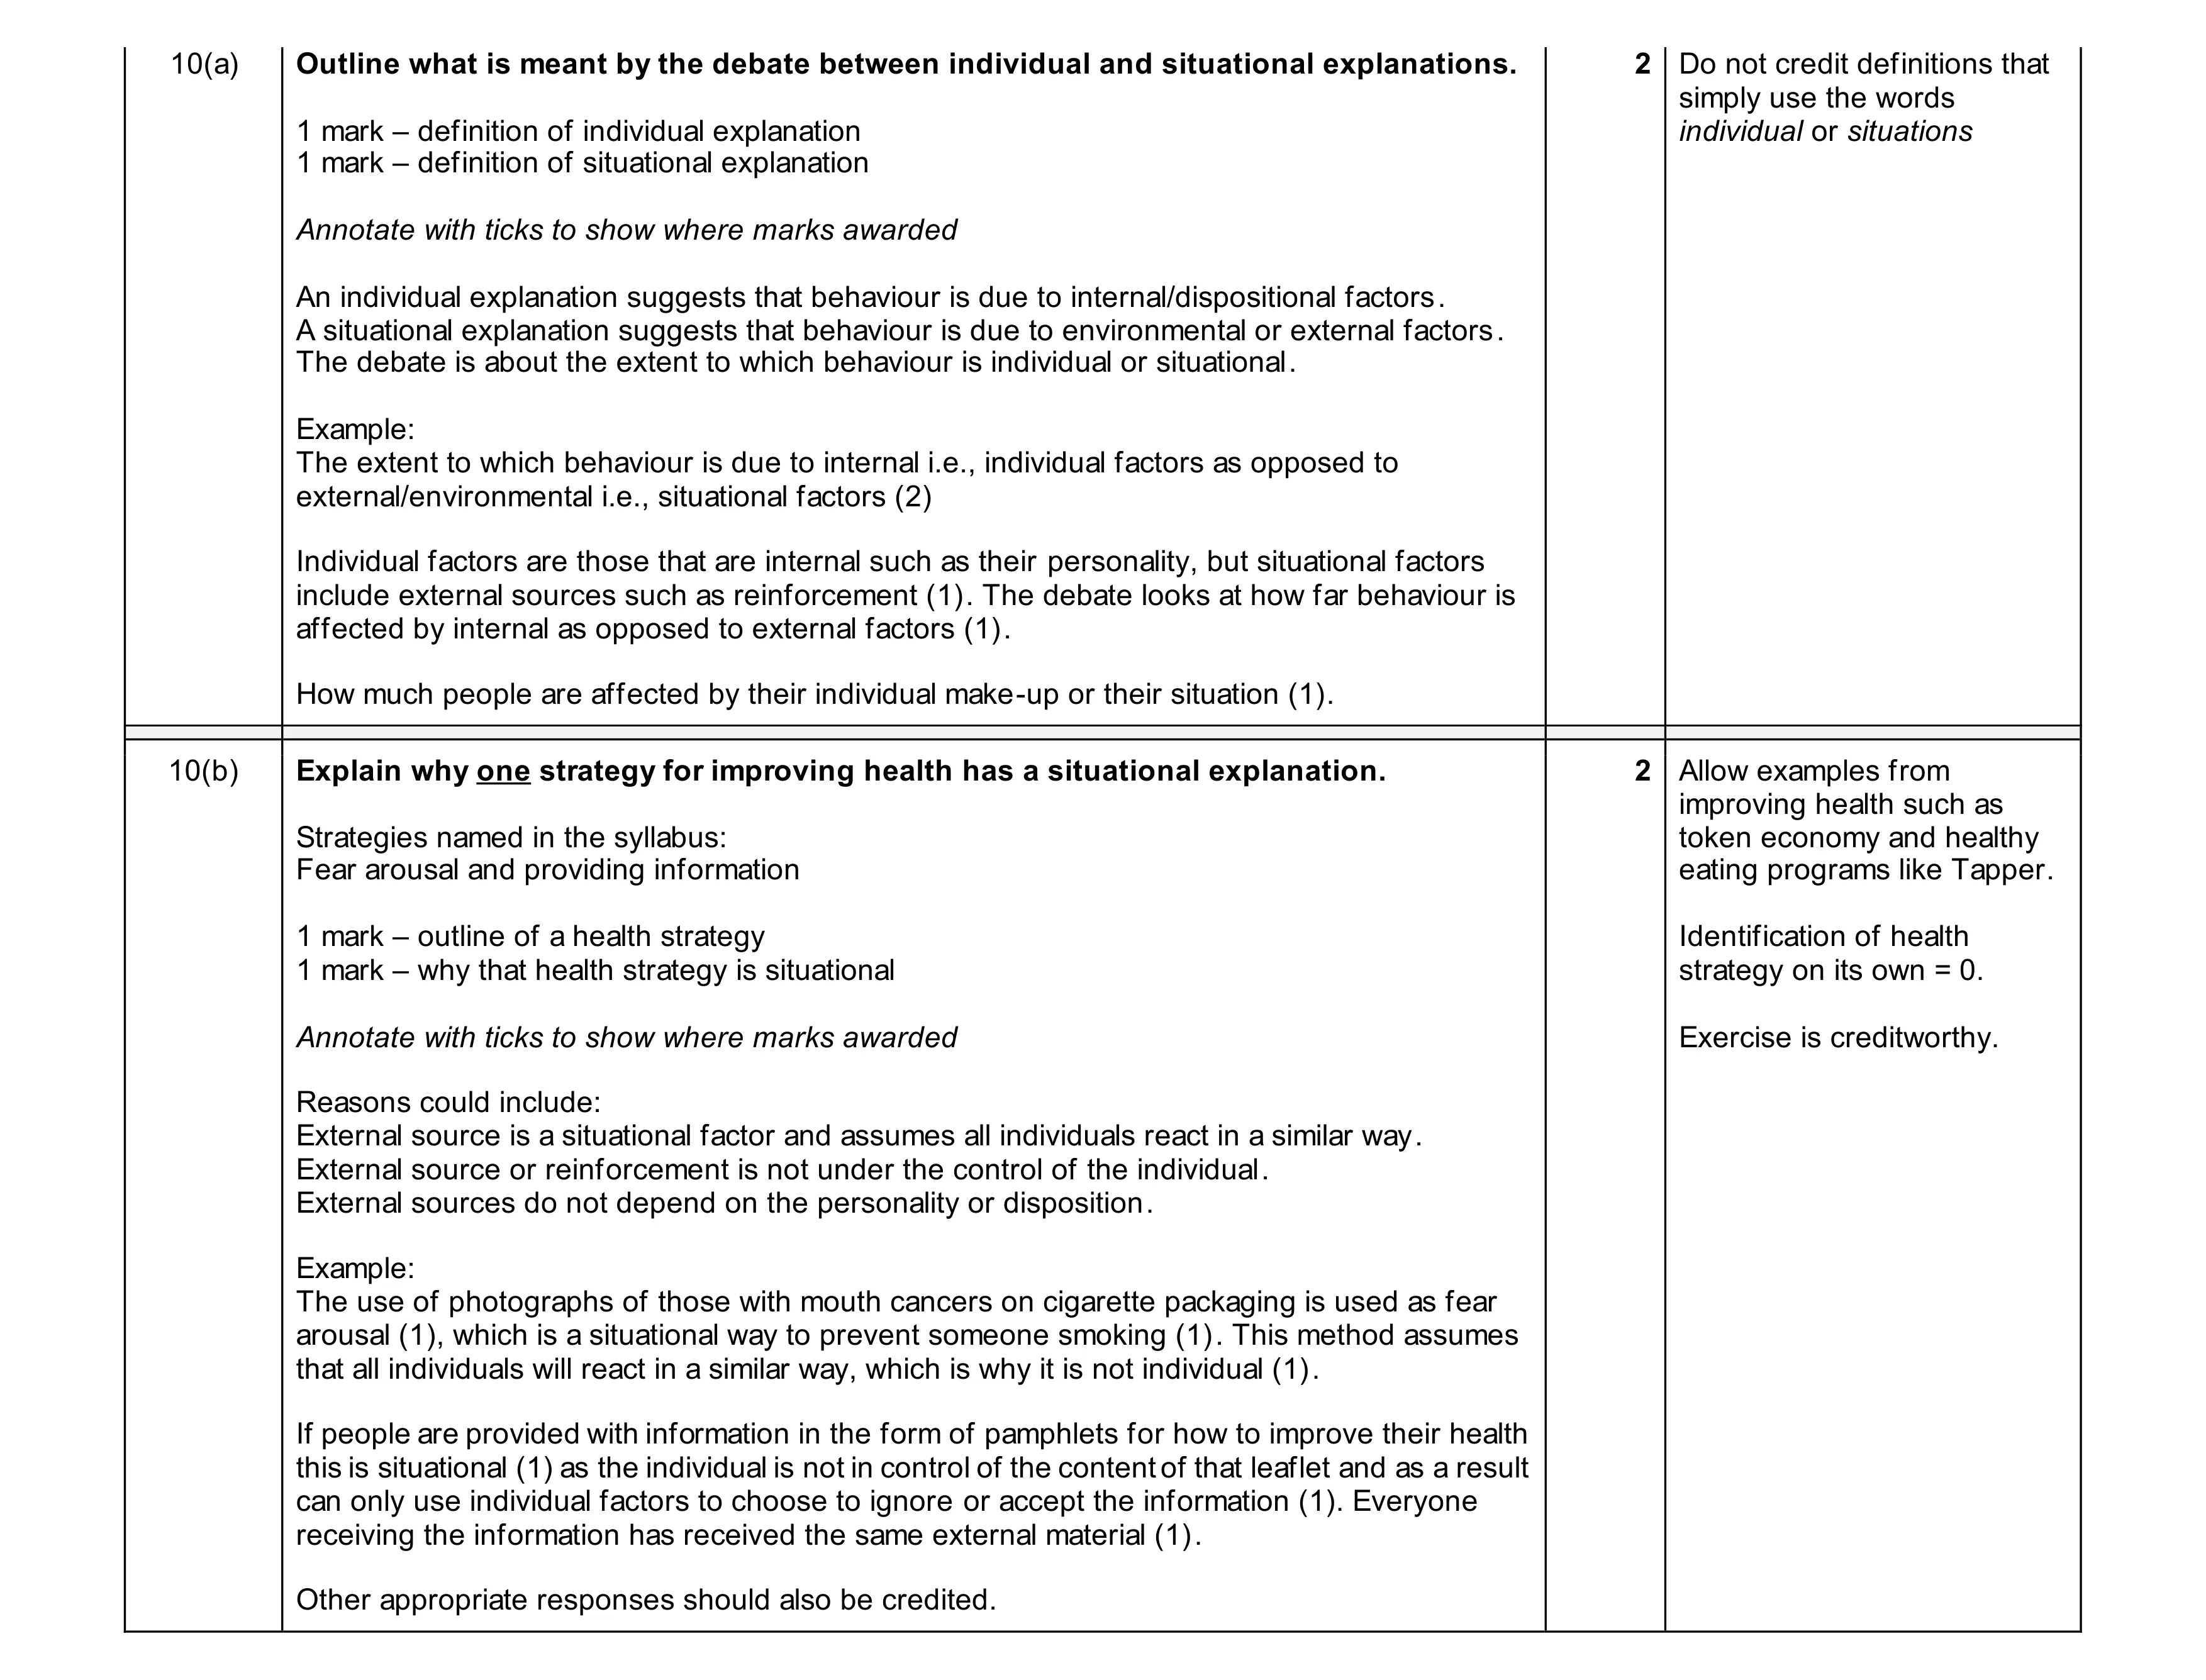 4
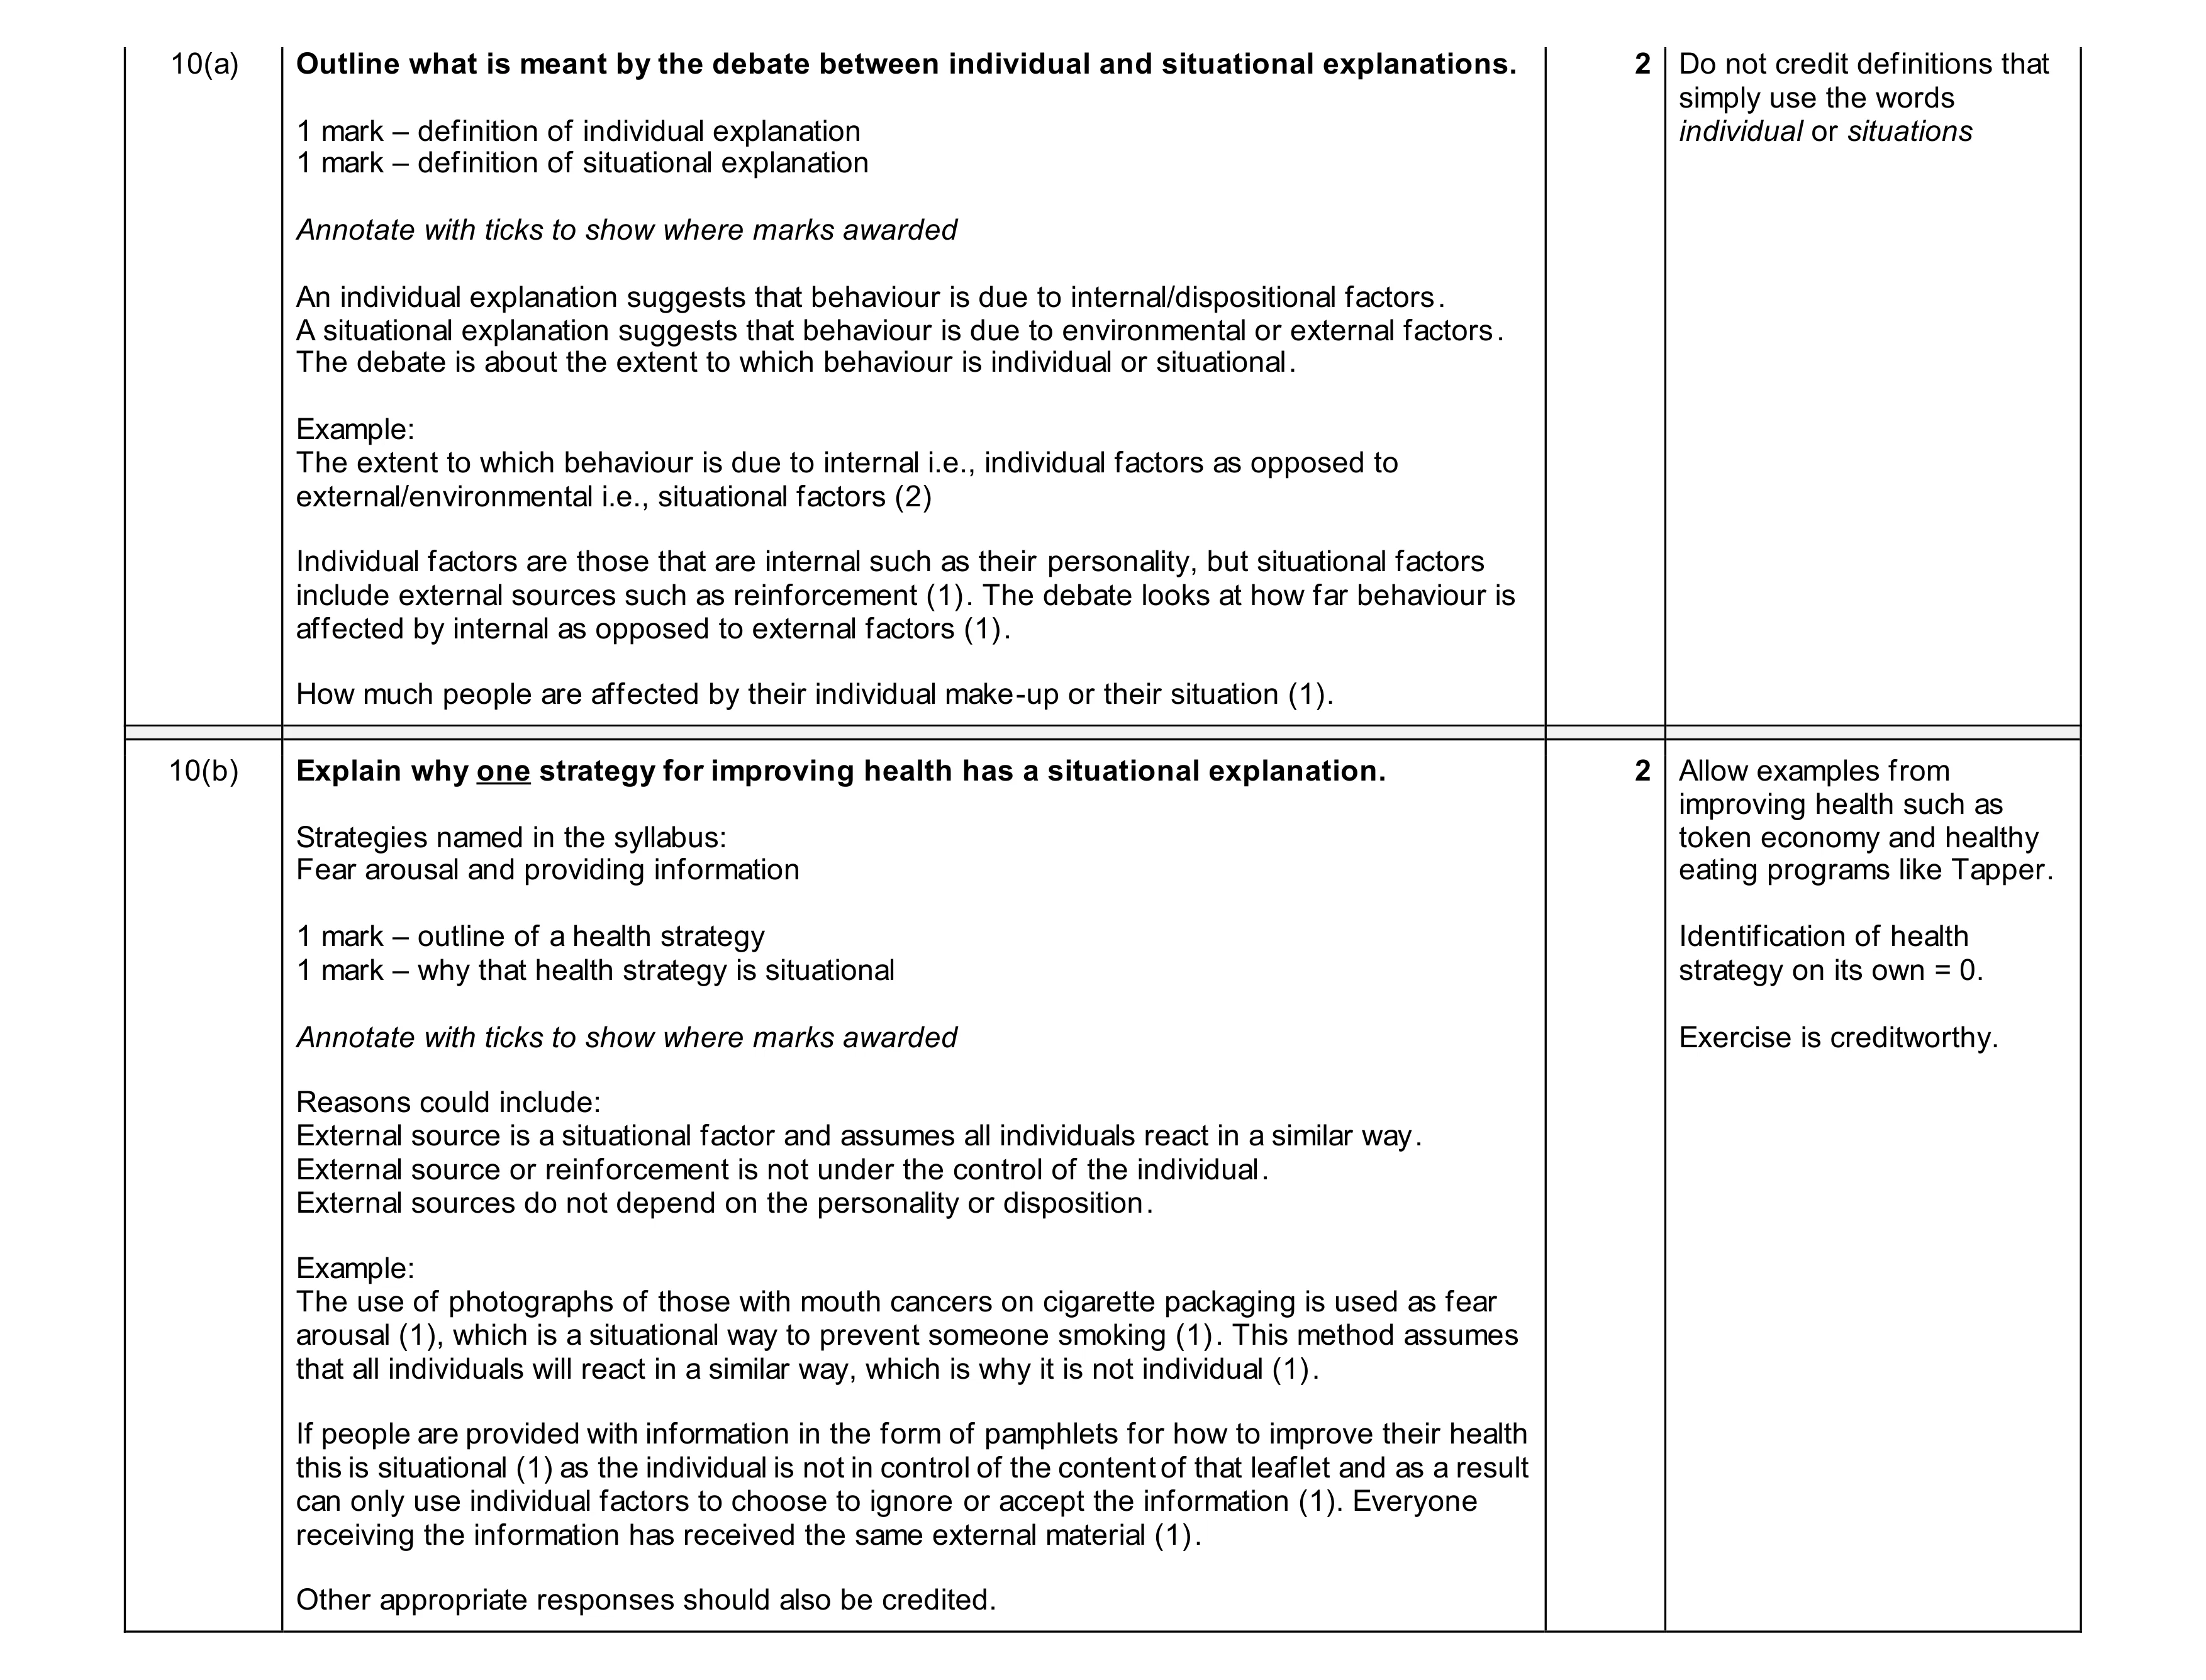 4